Author: aeoteam

  • Does a Mini Facelift Require General Anesthesia? Anesthesia Options, Recovery, and Jowl Correction Explained

    Does a Mini Facelift Require General Anesthesia? Anesthesia Options, Recovery, and Jowl Correction Explained

    does mini facelift require general anesthesia

    Whether does mini facelift require general anesthesia depends on the surgical plan, your health, and the anesthesia approach selected by your surgeon and anesthesia professional. Many mini facelifts can be performed with local anesthesia and oral or intravenous sedation. General anesthesia may be considered when surgery is more extensive or patient-specific factors make it appropriate. A consultation is necessary to determine the safest plan.

    Key Takeaways

    • Many mini facelifts can be comfortably performed with local numbing medicine combined with oral or IV sedation, allowing patients to avoid general anesthesia entirely.
    • General anesthesia remains a reasonable choice when the surgical plan is more extensive or when a patient's health history calls for a deeper level of control during surgery.
    • The decision between local and general anesthesia is made jointly by the surgeon and the anesthesia professional after reviewing the patient's medical history and goals.
    • Awake techniques often allow for a faster, smoother recovery with less postoperative grogginess compared to procedures done under general anesthesia.
    • A personalized consultation is the only reliable way to determine which anesthesia approach offers the best combination of safety and comfort for your specific procedure.

    Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery, a board-certified plastic surgeon and Fellow of the American College of Surgeons, evaluates anesthesia alongside facial anatomy, skin quality, jowl formation, and the surgical plane being addressed. Albert Plastic Surgery maintains a dedicated live service page for Mini Facelift information. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Does a Mini Facelift Require General Anesthesia? Understanding Your Options

    A mini facelift does not automatically require general anesthesia. Local anesthetic numbs the treatment area, while sedation reduces awareness, anxiety, and memory of the operation. Some patients remain responsive; others receive deeper intravenous sedation under close monitoring. General anesthesia creates a fully unconscious state and may be selected when the operation, medical history, or patient comfort makes it more suitable.

    The Primary Question: Anesthesia for a Mini Facelift

    The phrase does mini facelift require general anesthesia often reflects concerns about nausea, grogginess, breathing support, and recovery-room time. Anesthesia decisions depend on planned incisions, tissue elevation, operative duration, pain-control needs, medications, allergies, sleep or breathing history, and surgical-facility standards. A qualified anesthesia professional should review these factors before surgery.

    What Is a Mini Facelift and Who Is It For?

    A mini facelift is a focused facial rejuvenation operation for early to moderate laxity in the lower face and jawline. Depending on anatomy, the surgeon may elevate and secure deeper supporting tissue instead of relying only on skin tension. This can address some jowling and loose tissue, but not every sign of facial aging. It may not suit substantial neck laxity, advanced skin excess, certain medical conditions, or expectations beyond the procedure’s scope.

    Setting Realistic Expectations from the Outset

    A natural result requires proportionate correction, careful tissue handling, and acceptance of normal healing. Swelling, bruising, tightness, altered sensation, and incision visibility can occur even when surgery proceeds as planned. Early photographs are not a reliable measure of final appearance. The goal is not a frozen or windblown look, and no anesthesia method guarantees a particular cosmetic outcome. Discuss your priorities, concerns, and recovery tolerance during an in-person evaluation.

    Anesthesia Choices for Mini Facelift Surgery: A Clinical Comparison
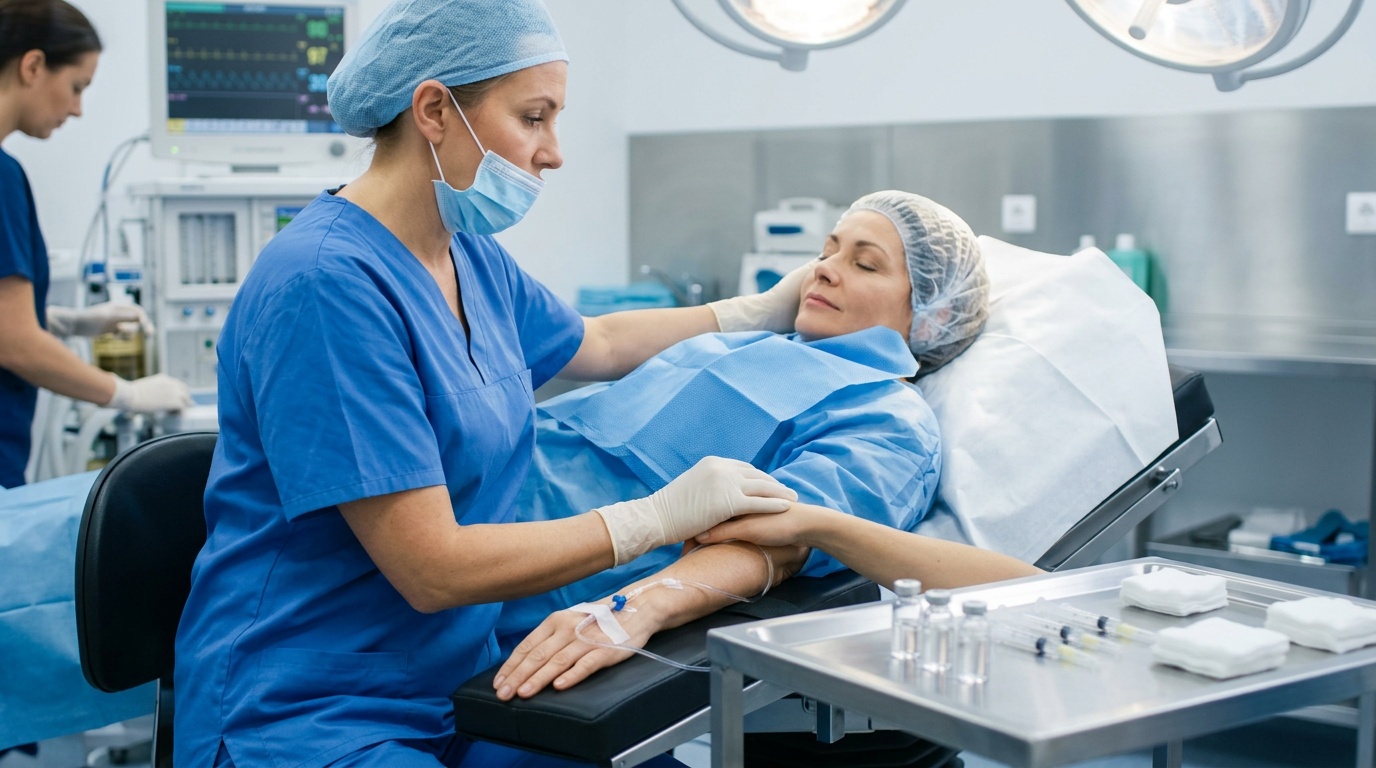
    Anesthesia Choices for Mini Facelift Surgery: A Clinical Comparison

    Local Anesthesia with Sedation: The Most Common Approach

    Local anesthesia with oral or intravenous sedation is frequently used for outpatient facial surgery. Local medication blocks sensation in the operative area, while sedation promotes relaxation. Depending on dose, you may be awake and responsive or lightly drowsy with limited memory afterward. This approach may avoid some effects associated with full unconsciousness, but it still requires monitoring, trained personnel, oxygen support when needed, and management of blood pressure, heart rate, and comfort.

    Intravenous Sedation (MAC): Deeper Relaxation, Conscious State

    Monitored anesthesia care, commonly called MAC, uses intravenous medication adjusted throughout surgery. The patient may remain responsive, with deeper relaxation than minimal oral sedation. Airway reflexes are generally maintained more than with general anesthesia, though breathing can still slow or become less effective. Continuous observation is essential. The anesthesia professional may adjust or stop medication according to important signs, responsiveness, and surgical requirements. The experience differs among patients.

    General Anesthesia: When It Might Be Considered

    General anesthesia produces unconsciousness and commonly involves airway management by an anesthesia professional. It may be considered for a longer or broader operation, difficulty remaining responsive, or patient-specific medical and psychological factors. Possible concerns include postoperative nausea, sore throat, temporary grogginess, blood pressure changes, medication reactions, and breathing complications. General anesthesia is not inherently inappropriate, but a mini facelift does not automatically need it. The surgical and anesthesia teams decide after reviewing your health and procedure.

    Comparing Anesthesia Options: Safety, Sensation, and Recovery

    There is no universally safest method for every patient. A responsible plan matches anesthesia depth to the operation and uses an accredited facility, appropriate monitoring, emergency equipment, and qualified personnel. Ask who administers the anesthetic, where surgery takes place, how airway concerns are managed, which medications are included, and what discharge criteria apply. Local anesthesia with sedation can allow a more alert recovery, while general anesthesia provides complete unconsciousness. Both require informed consent and attention to individual risks.

    Approach What you may experience Potential recovery considerations Questions to ask
    Local anesthesia with sedation The face is numb; relaxation ranges from mild drowsiness to limited awareness. Some patients have less grogginess, but monitoring and an escort remain necessary. What level of sedation is planned, and how will comfort be assessed?
    Intravenous sedation, or MAC Deeper relaxation with possible responsiveness and reduced memory. Medication can be adjusted during surgery; breathing and circulation require continuous observation. Who provides anesthesia, and what airway support is available?
    General anesthesia Complete unconsciousness with airway support managed by an anesthesia professional. Grogginess or nausea may occur, and discharge requires recovery from the anesthetic as well as stable important signs. Why is this depth appropriate for my operation and medical history?

    When patients ask, does mini facelift require general anesthesia, the accurate answer is that anesthesia is part of a personalized surgical plan, not a fixed feature of the procedure name. The selected method should support safety, surgical precision, comfort, and appropriate postoperative observation.

    Mini Facelift Techniques: Addressing Jowls and Lower Face Aging

    Understanding Lower Face Aging: Jowls and Jawline Laxity

    Jowls develop as skin loses elasticity, facial fat shifts, and connective tissue supporting the lower face becomes less firm. This may cause folds near the mouth, softening along the jawline, and tissue hanging below the mandibular border. Sun exposure, genetics, age, weight changes, and skin quality influence the pattern. A mini facelift addresses selected lower-face laxity; the operation depends on skin excess, the SMAS layer, and whether aging extends beyond the lower face.

    Why Non-Surgical Treatments Often Fall Short for Structural Jowl Correction

    Energy-based treatments, injectable products, threads, and skin-care programs may affect texture or provide temporary changes for selected patients. They cannot reliably reposition descended facial support structures as surgery can. A person may see modest skin-quality improvement yet remain dissatisfied with persistent mini face lift jowls or a blurred jawline. Repeated treatment can add expense without addressing the anatomic source. An in-person assessment distinguishes loose skin, displaced soft tissue, volume changes, and skeletal anatomy.

    The Mini Facelift Technique: SMAS Elevation vs. Skin-Only Tightening

    A skin-only lift places tension mainly on the outer skin envelope. It may initially look tighter, but excessive tension can contribute to a pulled or windblown look, widened scars, and recurrent laxity. A well-planned Mini Facelift may address the SMAS, a deeper connective-tissue layer supporting the lower face. SMAS elevation or repositioning can reduce dependence on skin tension. The maneuver may range from limited elevation to more involved dissection based on anatomy and jowling.

    Incision Patterns and Scarring Considerations in a Mini Facelift

    Incisions are commonly placed around the ear. Design depends on hairline position, skin excess, tissue movement, and technique. Some patients may have shorter incisions; others need additional access to release and secure lax tissue. Scars are permanent, though they generally mature and become less noticeable. Infection, delayed healing, unfavorable scarring, skin injury, asymmetry, nerve-related changes, and recurrent laxity remain possible risks. Technique should prioritize tissue integrity and balance rather than incision length alone.

    What This Technique May and May Not Address

    Pros

    • Can directly reposition selected lax tissues along the lower face and jawline.
    • May reduce jowling more predictably than treatments affecting only the skin surface.
    • Allows the surgeon to tailor dissection and SMAS treatment to individual anatomy.

    Cons

    • Does not stop normal aging or correct every neck and facial concern.
    • Involves incisions, swelling, bruising, sensory changes, and surgical risks.
    • Results vary with skin elasticity, healing, sun exposure, age, and operation.

    Realistic Mini Facelift Recovery: What to Expect by Day 5 and Beyond

    The Immediate Post-Operative Period: Day 1

    During the first day, the face may feel tight, numb, swollen, or tender. Bruising can become more noticeable over the next several days. Dressings, incision care, head elevation, activity restrictions, and medication instructions vary by surgeon and plan. Discharge should include a designated adult, clear instructions, clinical-team access, and warning signs. Do not drive, make important decisions, or judge the cosmetic result while affected by anesthesia or prescribed medication.

    Navigating Day 5: Swelling, Bruising, and Early Comfort

    Swelling commonly peaks between 48 and 72 hours, according to recovery information published by Dr. NeSmith. By Day 5, some patients notice early stabilization, but edema, bruising, tightness, and unevenness may remain. Mini facelift pictures after 5 days are not final comparisons. Lighting, camera angle, makeup, filters, and individual healing can mislead. Numbness near the ears or cheeks may persist and does not automatically indicate a poor result.

    The First Few Weeks: Suture Removal and Initial Healing

    Follow-up visits let the surgeon inspect incisions, assess swelling, and remove sutures when appropriate. Timing depends on closure technique and healing. Avoid strenuous activity, facial pressure, smoking, and unapproved products near incisions. Mild asymmetry can change as swelling resolves at different rates. Increasing redness, drainage, worsening pain, fever, sudden swelling, skin discoloration, shortness of breath, or new weakness requires prompt contact with the surgical team or urgent medical evaluation.

    Longer-Term Recovery: Sensation Changes and Returning to Normal

    Many patients gradually resume social and work activities as bruising subsides, guided by the surgeon. Facial sensation may remain altered for weeks or longer as sensory nerves recover. Incisions can look pink, firm, or uneven before scars mature. Tissue settling continues after the early period, so Day 5 or several weeks cannot establish success. A mini facelift may provide lasting improvement, but future aging, environmental exposure, and inherited skin characteristics continue to affect the face.

    Preventing Poor Outcomes: Surgeon Expertise and Patient Adherence

    Concerns about a botched mini face lift include visible scarring, distortion, asymmetry, skin compromise, recurrent laxity, or injury to facial nerve branches. Risk reduction begins with an appropriately trained, board-certified plastic surgeon who understands facial anatomy and selects a suitable technique. Facility accreditation, qualified anesthesia personnel, sterile protocols, emergency readiness, and structured follow-up also matter. Patients support healing by accurately disclosing medical history and medications, following wound-care instructions, keeping appointments, and reporting changes early. No credential or protocol eliminates every risk, and outcomes cannot be not assured.

    Making an Informed Decision: Consultation, Costs, and Candidacy

    Making an Informed Decision: Consultation, Costs, and Candidacy

    When asking does mini facelift require general anesthesia, also consider whether the operation matches your anatomy and goals. A consultation with a board-certified plastic surgeon should assess skin elasticity, lower-face laxity, jowl formation, medical history, medications, smoking status, and recovery preferences. Dr. Albert reviews these together rather than choosing anesthesia in isolation. Albert Plastic Surgery maintains a dedicated live service page for Mini Facelift education. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Who Is a Good Candidate for a Mini Facelift?

    A potential candidate may have early to moderate sagging around the cheeks, jawline, or jowls and want measured improvement rather than dramatic change. Good general health, realistic expectations, and willingness to follow postoperative instructions matter. A mini facelift may be less suitable with substantial neck laxity, extensive skin excess, untreated medical risk, or goals beyond the operation’s scope. Age alone does not determine eligibility; facial structure, tissue quality, healing capacity, and priorities are more informative.

    Key Questions to Ask Your Surgeon About Anesthesia and Technique

    Ask which tissue layers will be addressed, whether the plan includes SMAS repositioning, where surgery will occur, who will administer anesthesia, and what monitoring and emergency resources are available. Discuss incision design, hairline and ear anatomy, follow-up, warning signs, and unretouched procedure-specific photographs showing healing stages. Online mini facelift reviews cannot replace an examination or discussion of your risk profile.

    Understanding the Financial Investment: Surgeon, Facility, and Anesthesia Fees

    When considering how much does a mini facelift cost, request a written estimate separating the surgeon’s fee, facility charge, anesthesia services, preoperative evaluation, postoperative visits, and supplies. Pricing varies with complexity, anesthesia depth, geographic location, facility standards, and surgeon experience. A low quote may exclude necessary services, while a higher quote does not guarantee a particular result. Ask which charges are included, what happens if the plan changes, and whether revision surgery or complication treatment has separate fees.

    The Longevity of Mini Facelift Results

    Patients often ask how long does a mini facelift last. Published patient education from Healthline describes results as lasting for several years. Duration varies with skin elasticity, age, sun exposure, genetics, weight fluctuations, and the depth of tissue support addressed. Surgery does not stop future aging. A thoughtful plan aims for natural improvement that remains proportionate as the face changes, rather than promising permanence.

    Next Steps: Scheduling Your Personalized Consultation

    A consultation is the appropriate next step to determine whether a mini facelift can address your lower-face concerns. Confirm the surgeon’s American Board of Plastic Surgery certification, Fellow of the American College of Surgeons status, facility accreditation, anesthesia arrangements, and postoperative access. Bring a complete medical history and discuss timing, privacy needs, and tolerance for visible healing. The final answer to does mini facelift require general anesthesia should follow this individualized review, not a generalized online promise.

    Frequently Asked Questions

    How painful is a mini facelift?

    A mini facelift usually involves manageable discomfort rather than severe pain, though each patient’s experience varies. Local anesthesia or sedation helps control discomfort during surgery, while swelling, bruising, tightness, and altered sensation may occur during healing. Dr. Albert reviews pain-control options and recovery concerns during an individualized consultation.

    Can you get a mini facelift without general anesthesia?

    A mini facelift can often be performed with local anesthesia and oral or intravenous sedation instead of general anesthesia. The appropriate approach depends on the surgical plan, medical history, medications, breathing history, comfort level, and facility standards. A qualified anesthesia professional and surgeon should determine the safest option for each patient.

    How long does it take to look normal after a mini facelift?

    A mini facelift may require several weeks for swelling, bruising, tightness, and altered sensation to settle, while final healing can take longer. Recovery varies with surgical technique, anatomy, skin quality, and individual healing. Early photographs may not reflect the final appearance, so follow-up with the surgeon is important.

    How does a 60-year-old look before and after a mini facelift?

    A 60-year-old may have improvement in selected lower-face laxity, jowling, or jawline definition after a mini facelift, though results vary substantially. Before-and-after appearance depends on facial anatomy, skin quality, tissue support, surgical technique, and healing. A mini facelift may not address significant neck laxity or advanced skin excess.

    What are the downsides of a mini facelift?

    Mini facelift downsides can include swelling, bruising, tightness, temporary numbness, incision visibility, scarring, asymmetry, infection, bleeding, and dissatisfaction with the result. A mini facelift also has limits and may not correct substantial neck laxity or advanced facial aging. Individual risks, candidacy, and alternatives require an in-person clinical assessment.
    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 4, 2026 by the Albert Plastic Surgery Team
  • Mini Facelift vs Full Facelift: Key Differences Guide

    Mini Facelift vs Full Facelift: Key Differences Guide

    difference between mini facelift and full face lift

    The difference between mini facelift and full face lift depends on the location and degree of facial laxity, the tissues requiring support, and the result a patient hopes to achieve. A mini facelift may provide focused improvement for early jowling or limited lower-face laxity, while a traditional or deep plane facelift may address more extensive changes across the cheeks, jawline, and neck. Age alone does not determine the appropriate choice.

    This comparison is general education, not individualized medical advice. Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery reviews facial anatomy, skin quality, soft-tissue descent, and personal goals before recommending a surgical plan. Dr. Albert is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons.

    Understanding Facelift Differences: Mini vs. Full, and Beyond

    A Concise Answer: What Sets Facelifts Apart?

    A mini facelift generally uses a more limited approach to improve selected areas of the lower face. It may suit early jowls, mild cheek descent, or modest skin laxity. A full facelift typically offers broader access and more extensive repositioning of facial tissues for pronounced laxity, deeper folds, or changes extending toward the jawline or neck. The difference between mini facelift and full face lift includes treatment area, incision design, tissue support, recovery demands, and the degree of visible change possible.

    Why “Mini” and “Full” Aren’t Always Standardized

    “Mini facelift” and “full facelift” describe procedures rather than universally defined operations. Surgeons may use different incision patterns, tissue planes, suspension methods, and definitions. One surgeon’s mini facelift may involve more tissue work than another surgeon’s limited lift. Consultation should explain the facial zones treated, deeper layers repositioned, incision placement, and concerns outside the operation’s scope.

    The Core Goal: Addressing Facial Aging with Precision

    Facelift surgery addresses structural signs of aging, including descended cheek tissue, jowling, loose facial skin, and reduced jawline definition. It does not stop future aging, change every facial feature, or guarantee a particular appearance. Natural-looking surgery respects facial proportions and avoids excessive tightness. The question is which operation fits the patient’s anatomy without treating areas that do not require surgery.

    How We Evaluate Facelift Options for Your Unique Anatomy

    How We Evaluate Facelift Options for Your Unique Anatomy

    Our Approach: Anatomy, Goals, and Realistic Outcomes

    Facelift planning begins with an in-person examination rather than a procedure name. I assess cheek position, nasolabial and marionette folds, jowls, skin elasticity, facial volume distribution, and the relationship between the lower face and neck. We discuss how much change feels appropriate. Someone seeking subtle improvement may have different priorities from someone concerned about substantial tissue descent.

    Key Factors in Surgical Planning: Beyond Age

    Age is only one part of the assessment. Genetics, sun exposure, weight stability, skin behavior, bone structure, prior facial surgery, general health, and healing history can influence the plan. The difference between mini facelift and full face lift becomes clearer when these factors are considered together. A shorter operation or smaller incision is not automatically better if it cannot address the patient’s concerns.

    Consultation Essentials: What to Discuss with Your Surgeon

    A useful consultation should allow time for examination, questions, and discussion of limitations. Patients may wish to ask:

    • Which areas of my face show laxity, and which areas would the proposed lift treat?
    • What tissue layers would be repositioned, and why is that approach appropriate for my anatomy?
    • Where would incisions be placed, and how might scars mature?
    • What recovery restrictions, swelling, bruising, and follow-up care should I anticipate?
    • Which changes are realistic, and which concerns would remain after surgery?
    • What are the material risks, limitations, and reasons the plan might need to change?

    Candidacy, technique, anesthesia, recovery, risks, and outcomes require individualized clinical assessment. A qualified, board-certified plastic surgeon should explain these details directly and provide continuity of care before and after surgery.

    Comparing Your Facelift Choices

    Mini Facelift: Focused Improvement for Specific Concerns

    Best for: selected patients with early or limited lower-face laxity, mild jowling, or modest loss of jawline definition.

    Mini Facelift is directly within the client-directed facelift scope. It may use shorter incisions and a focused treatment area, though technique varies. Neck laxity, significant loose skin, and advanced descent may not be adequately addressed through a limited approach. The goal is proportional improvement, not simply the smallest operation.

    The Traditional Facelift: Addressing Broader Signs of Aging

    Best for: patients with established laxity involving the cheeks, lower face, jowls, and jawline.

    A traditional facelift generally permits broader access to facial tissues and more comprehensive skin redraping. The surgeon may work with deeper supporting structures rather than relying on skin tension alone. This can suit aging that is not confined to one region. Careful planning aims to preserve facial movement, expression, and individual character without creating a tight or excessive appearance.

    Full Facelift with Neck Lift: Comprehensive Rejuvenation

    Best for: patients whose aging extends from the midface and jawline into the neck.

    When the neck shows meaningful skin laxity or weakened contour, a broader facelift plan may include that region. Neck work depends on anatomy and goals. Patients should ask whether the operation addresses the transition from cheek to jawline to neck, rather than assuming every operation called “full” includes the same areas.

    Deep Plane Facelift: Advanced Tissue Mobilization

    Best for: selected patients whose facial aging may benefit from repositioning deeper soft-tissue layers as a connected unit.

    A Deep Plane Facelift involves a specific anatomic plane beneath selected facial retaining structures. Mobilizing deeper tissues may redistribute descent with less dependence on skin traction. This is an advanced technique, not a universal upgrade or automatic solution. Anatomy, surgeon training, tissue laxity, and desired change determine whether it is appropriate.

    Nanolift™: A Refined Approach within Our Practice

    Best for: carefully selected patients seeking a focused facelift approach based on their pattern of early aging.

    Nanolift™ and a mini facelift should not be selected by name alone. Within our practice, Nanolift™ refers to a refined approach planned around anatomy and the degree of correction needed. Its scope, tissue work, and expected recovery require direct discussion. The deciding factor is an accurate examination and a realistic understanding of what facelift surgery can and cannot accomplish.

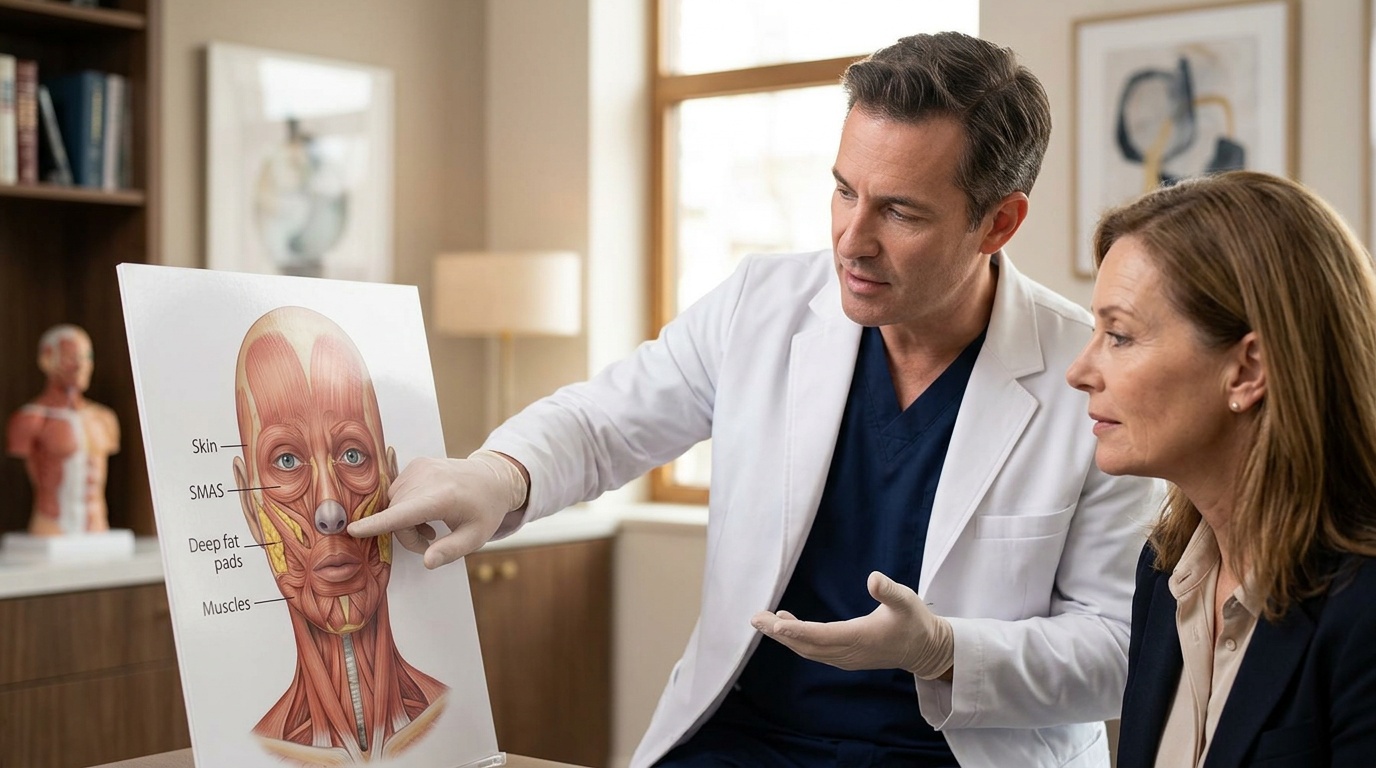
    Facelift anatomy is assessed from the cheek through the jawline and neck. The selected approach depends on tissue descent, skin elasticity, retaining structures, incision needs, and the patient’s goals.

    Facelift Procedure Comparison: Key Differences at a Glance

    The difference between mini facelift and full face lift is most apparent in treatment area, tissue support, incision pattern, and recovery. A limited operation may suit localized laxity, while a broader facelift may fit descent affecting the cheeks, jawline, and neck. Since procedure names are not standardized, the table offers a general framework rather than a substitute for examination.

    Treatment Areas and Tissue Work

    A Mini Facelift commonly concentrates on the lower face, including early jowling and mild jawline definition loss. It may not provide enough access for substantial neck laxity or extensive loose skin beneath the chin. A traditional facelift addresses a broader lower face and may reposition supporting tissues. A Deep Plane Facelift uses a deeper plane in selected patients, while Nanolift™ is planned within Albert Plastic Surgery according to the individual pattern of aging.

    Incision Placement and Scarring

    Incisions vary with technique, skin laxity, hairline and ear anatomy, and neck treatment. A mini approach may use a more limited incision, though a shorter scar does not necessarily mean a simpler operation or better result. Broader lifts require access for safe tissue repositioning and skin redraping. Scars are permanent marks that generally mature over time; their appearance reflects healing biology, placement, tension, and aftercare.

    Recovery Expectations and Downtime

    Recovery depends on dissection, tissue-plane technique, anesthesia, healing, and daily demands. A focused lift may involve less swelling or a shorter interruption of routine for some patients, but this cannot be assumed. Comprehensive surgery can produce more bruising, swelling, tightness, and temporary sensory changes. Patients should plan for follow-up, activity restrictions, incision care, and a gradual return to work and social activities.

    Longevity and Continued Aging

    The visible benefit of any facelift changes as normal aging continues. Skin quality, genetics, sun exposure, weight fluctuations, and degree of correction influence later changes. A broader operation may address more extensive laxity, while a limited lift may suit localized concerns. Neither stops aging or guarantees permanence. The key question is whether tissue correction matches current anatomy and long-term expectations.

    Potential Risks and Limitations

    Risks include bleeding, infection, adverse scarring, delayed healing, sensory changes, asymmetry, contour irregularity, hair or skin changes, nerve injury, revision surgery, and anesthesia or medical complications. A mini facelift is not automatically lower-risk because its incision or treatment area is smaller, and a full facelift is not inherently unnatural when appropriately planned. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Consideration Mini Facelift Traditional or Full Facelift Deep Plane Facelift Nanolift™
    Typical scope Focused lower-face laxity and early jowling Broader cheek, jawline, and lower-face aging Selected patterns requiring deeper tissue mobilization Refined, anatomy-specific correction within the practice
    Neck concerns May be limited for substantial neck laxity May address the neck when included in the surgical plan Neck treatment depends on the overall design Scope is determined during consultation
    Incision and tissue work Often more limited, with technique variation Broader access and skin redraping Work through a deeper facial plane Focused approach selected for the patient’s anatomy
    Recovery considerations May involve less extensive swelling, not not assured More areas may require healing and observation Recovery varies with tissue mobilization and extent Individualized expectations and follow-up

    Making Your Informed Decision: What Matters Most

    Making Your Informed Decision: What Matters Most

    When a Mini Facelift May Be Considered

    A mini facelift may suit aging concentrated in the lower face, with early jowling, mild laxity, or limited jawline definition loss. It may be reasonable for focused correction when the neck and midface do not require broader treatment. A shorter incision or limited operation is not automatically right; the lift must adequately support the treated tissues.

    When a Traditional or Deep Plane Facelift Might Be Appropriate

    A traditional facelift or Deep Plane Facelift may suit widespread descent involving the cheeks, lower face, jowls, and possibly neck. Choice depends on tissue plane, skin elasticity, retaining ligaments, facial proportions, and desired change. The difference between mini facelift and full face lift is best evaluated through these anatomic details, not presumed age or a wish for the least extensive procedure.

    The Role of Combined Procedures

    When aging extends across connected areas, a plan may address more than one region in the same operation. Patients should ask which areas are included, why each is treated, and how the plan affects anesthesia, incision care, swelling, activity restrictions, and follow-up. Combined treatment must reflect medical history, safety, and clear understanding of the tradeoffs.

    Understanding Realistic Expectations and Limitations

    Facelift surgery can reposition descended soft tissue and remove or redrape selected loose skin. It cannot stop aging, correct every concern, or guarantee a specific appearance. A natural result should remain consistent with anatomy and expression. Scars, swelling, altered sensation, asymmetry, and possible residual laxity should be discussed before consent.

    Navigating Post-Procedure Care and Long-Term Results

    Recovery requires incision care, examinations, activity limits, and patience as swelling settles. Instructions vary with the operation and healing pattern. Long-term results also reflect genetics, skin behavior, sun exposure, weight changes, and continued aging. Follow-up with the operating surgeon helps identify concerns early and supports decisions about future care.

    Frequently Asked Questions About Facelift Surgery

    Can a mini facelift address neck laxity?

    It may provide limited improvement when neck changes are mild, but a focused lift may not adequately treat substantial loose skin or muscle laxity. The answer depends on examination.

    Will a facelift look unnatural?

    Technique, tissue support, skin redraping, and planning influence appearance. A facelift is not intended to create excessive tightness, though no surgeon can guarantee a particular result.

    How long does recovery typically take for each type?

    Recovery varies with surgical extent, anesthesia, tissue handling, health, and healing. A limited procedure may involve less downtime for some patients, while broader surgery can involve more swelling and restrictions.

    What are the main risks associated with facelift surgery?

    Risks include bleeding, infection, delayed healing, visible scarring, sensory changes, asymmetry, contour irregularity, nerve injury, anesthesia complications, and revision surgery.

    How do I choose a qualified facelift surgeon?

    Confirm American Board of Plastic Surgery certification, review training and facelift experience, and ask about anatomy, technique, risks, recovery, and follow-up. Dr. Albert is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. Consultation is necessary to determine whether any facelift approach suits your needs.

    Frequently Asked Questions

    What are the downsides of a mini facelift?

    Mini facelift downsides can include limited correction, visible scarring, surgical risks, and the possibility that neck laxity or advanced facial descent remains. A mini facelift may not provide the broader tissue support possible with a traditional or deep plane facelift. Candidacy, technique, recovery, risks, and expected outcomes require an individualized consultation.

    What is the most natural-looking facelift?

    The most natural-looking facelift is the procedure that matches a patient’s anatomy, degree of laxity, and desired amount of change. Mini, traditional, and deep plane facelifts can all produce natural-looking results when facial tissues are repositioned appropriately rather than pulled excessively. Outcomes vary, and no technique guarantees a particular appearance.

    What is the average cost of a mini facelift?

    The average cost of a mini facelift varies according to surgical technique, anesthesia, facility fees, geographic location, and the areas treated. A limited facelift may not include neck surgery or other procedures that affect the total fee. A consultation with a qualified plastic surgeon provides a personalized estimate and a discussion of risks and limitations.

    What is the best age for a mini facelift?

    The best age for a mini facelift depends on facial laxity, skin quality, health, and personal goals rather than a specific number. Mini facelifts may suit selected patients with early jowling or limited lower-face laxity. An in-person examination is needed to determine whether a mini facelift or broader operation fits the anatomy.

    What procedure takes 10 years off your face?

    No facelift procedure can reliably or permanently take 10 years off a person’s face. A mini facelift, traditional facelift, deep plane facelift, or facelift with neck work may address selected signs of facial aging, though results and longevity vary. Dr. Albert evaluates facial structure, tissue descent, skin quality, and goals before recommending a plan.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 3, 2026 by the Albert Plastic Surgery Team
  • Deep Plane Vertical Facelift: Surgical Anatomy, Vectors, and Results

    Deep Plane Vertical Facelift: Surgical Anatomy, Vectors, and Results

    deep plane vertical facelift

    A deep plane vertical facelift addresses facial aging by repositioning deeper facial tissues upward rather than relying primarily on skin tightening. The goal is to restore the relationship among the cheek, jawline, jowls, and neck while limiting skin tension. This approach may help avoid a windswept appearance, visible distortion, or artificial fullness, though candidacy and technique require an in-person evaluation.

    Key Takeaways

    • The deep plane technique releases and lifts tissues beneath the SMAS layer, which allows the cheek and midface to move as a unified structure instead of relying on tension at the skin level.
    • A vertical vector may redirect descended tissue upward and may improve cheek contour, jawline definition, and jowls; incision and tissue movement can affect hairline or ear position depending on the operation.
    • Placing the lift on deeper support layers rather than the skin itself helps results look rested and natural instead of pulled, windswept, or overly full.
    • Most patients experience swelling and bruising during the first two weeks, with a gradual return to social activities and exercise over the following weeks.
    • The best candidates show meaningful descent of the cheek and jawline, and an in-person examination is required to confirm that this approach matches your anatomy and goals.

    Understanding the Deep Plane Vertical Facelift: A Foundation for Natural Rejuvenation

    What Is a Deep Plane Vertical Facelift?

    A deep plane vertical facelift mobilizes skin with the superficial muscular aponeurotic system, commonly called the SMAS, and selected deeper soft tissues. The surgeon releases retaining ligaments that tether these layers to the facial skeleton. The composite tissue envelope can then move upward with less dependence on skin traction.

    “Vertical” describes the principal direction of repositioning. Aging tissues commonly descend downward and inward, producing cheek flattening, deeper folds beside the nose and mouth, jowls, and a less defined jawline. An upward vector more closely follows the direction in which youthful facial support is restored than a predominantly lateral pull.

    The Evolution: From Traditional Facelifts to Vertical Deep Plane Techniques

    Earlier facelift methods often focused on removing excess skin and applying surface tension. Modern deep plane surgery developed from the anatomical work of Sam Hamra, including his foundational 1990 description of deeper facial tissue mobilization. Current techniques emphasize the SMAS, facial ligaments, tissue planes, and the direction of elevation.

    Terminology varies among surgeons. Deep plane, high SMAS, and vertical techniques may describe different operative plans, and the names alone do not establish how a surgeon will perform the operation. Consultation should cover the intended dissection plane, ligament release, vector, incision design, anesthesia plan, and limits of correction. Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery evaluates these factors individually as a board-certified plastic surgeon and Fellow of the American College of Surgeons.

    Addressing the Core of Facial Aging: Beyond Skin-Deep

    Facial aging involves more than loose skin. The cheek fat compartment may descend, ligament attachments may become more apparent, and the lower face may lose definition. Repositioning deeper tissues can address this structural descent more directly than skin excision alone. It does not erase every wrinkle, change skin texture, reverse sun damage, or correct all fine lines. Skin quality, facial volume, bone structure, and natural asymmetry remain relevant.

    The Anatomical Blueprint: How Vertical Lifting Works

    The Anatomical Blueprint: How Vertical Lifting Works

    The Role of Facial Retaining Ligaments: Key Release Points

    Retaining ligaments connect facial soft tissue to deeper structures and help maintain facial contours. With age, they can contribute to fixed folds and resistance to upward movement. Deep plane dissection may selectively release the zygomatic retaining ligaments in the cheek and masseteric retaining ligaments along the lower face. The composite flap can then move as a unit, reducing the need to stretch skin independently.

    Ligament release requires knowledge of facial anatomy. The surgeon must account for branches of the facial nerve, the parotid region, blood supply, fat compartments, and the thickness of each tissue layer. The release pattern varies with facial structure, prior surgery, tissue descent, and the desired distribution of lift.

    Sub-SMAS Dissection: Mobilizing Deeper Tissues

    The SMAS is a fibrous layer connected with facial muscles and soft tissue. A sub-SMAS approach places dissection beneath this layer, allowing mobilization of tissue that a skin-only operation cannot reach. The purpose is not indiscriminate fullness, but repositioning descended tissue toward a more appropriate relationship with the cheek, nasolabial region, jawline, and neck. For an overview of the procedure, see the deep plane facelift procedure.

    Illustrative anatomy: a deep plane operation may include sub-SMAS mobilization and release of selected zygomatic and masseteric retaining ligaments. Actual anatomy and operative planes differ by patient and require direct clinical assessment.

    The Vertical Vector: Respecting Natural Anatomy and Gravity

    A vertical vector directs movement upward, often supporting the midface and jowl region without concentrating force at the temples or preauricular skin. Research discussed in Facial Plastic Surgery literature has reported approximately twice the anatomical elevation in these regions with vertical vectors compared with diagonal pull vectors. This is anatomical research, not a guarantee of an individual result.

    Vector selection remains individualized. A surgeon may use different directions across facial zones because the cheek, lower face, and neck do not age in precisely the same way. The objective is proportion, not maximal movement. Excessive tension or an overly uniform vector can contribute to an unnatural expression, hollowing, or distortion.

    Restoring the Midface and Lower Face Architecture

    As cheek soft tissue descends, the lower-eyelid-to-cheek transition may lose support, while the nasolabial fold and jowl become more pronounced. Upward mobilization can improve midface and lower-face continuity by repositioning the tissue envelope. It may also improve jawline contour when laxity is driven by descent rather than skin quality alone.

    Anatomical feature Surface-focused lift Deep plane vertical approach
    Primary tissue acted upon Skin and superficial support Composite skin and SMAS-related tissue
    Movement direction Often lateral or diagonal Predominantly upward, adjusted by facial region
    Ligament treatment May leave deeper tethering intact May release selected zygomatic and masseteric attachments
    Primary anatomical aim Reduce visible skin laxity Reposition descended facial architecture with less skin tension

    Patient Candidacy and Realistic Expectations for Vertical Deep Plane Facelifts

    Who Is a Candidate for Vertical Deep Plane Facelift?

    A vertical deep plane facelift may suit an adult with visible descent of the cheek, jowls, lower face, or neck, particularly when laxity reflects changes beneath the skin. Candidacy depends on facial anatomy, skin elasticity, medical history, prior procedures, healing capacity, and personal goals. A consultation with Dr. Albert assesses facial balance, tissue movement, retaining ligaments, asymmetry, and structural aging. Neither age nor a photograph establishes suitability.

    A more limited operation may be considered when laxity is localized. Albert Plastic Surgery maintains a dedicated Mini Facelift service page. A Mini Facelift is within the client-directed facelift scope, yet it is not automatically interchangeable with a deeper operation. Candidacy, technique, recovery, risks, and outcomes require individualized assessment.

    What a Deep Plane Vertical Facelift Can Address, and What It Cannot

    By releasing selected facial attachments and repositioning the deeper tissue envelope upward, this operation may improve descended cheek contours, jowls, lower-face laxity, and some nasolabial fold prominence. It can support a more defined relationship among the midface, jawline, and neck. The degree of change depends on anatomy and tissue descent. A vertical vector restores position rather than creating maximum tightness.

    Surgery does not remove every fine wrinkle, correct sun damage, change skin texture, replace lost skeletal support, or stop future aging. It may not fully correct asymmetry or every crease around the mouth. Skin quality and facial volume remain separate considerations, and a qualified surgeon should explain which concerns are structural and which may remain after healing.

    Distinguishing Skin Quality from Structural Aging

    Structural aging involves descent of soft-tissue compartments, stretched ligamentous support, and changes in facial contour. Skin aging involves thinning, reduced elasticity, pigmentation, rough texture, and fine lines. Deep tissue repositioning addresses structural change more directly. Skin with limited elasticity may still show residual creasing after redraping, and removing additional skin does not necessarily restore youthful facial architecture.

    Setting Realistic Expectations: Avoiding Distortion and Unnatural Fullness

    A natural result depends on proportion, measured movement, and appropriate skin redraping. Excessive lateral traction can create a pulled or windswept appearance, while indiscriminate fullness can look unlike the patient’s normal anatomy. Vertical repositioning respects facial support, but it does not eliminate risks of contour irregularity, asymmetry, nerve injury, scarring, bleeding, infection, or an unsatisfactory result.

    Potential Benefits and Limitations

    Pros

    • Addresses selected deeper tissue descent rather than relying only on skin tension.
    • May improve cheek, jowl, and jawline relationships through upward repositioning.
    • Can support a proportionate appearance when the vector matches the patient’s anatomy.

    Cons

    • Does not erase all wrinkles, skin damage, or texture changes.
    • Requires detailed anatomical evaluation and an individualized surgical plan.
    • Involves operative risks, visible healing, swelling, scarring, and variable outcomes.

    The Surgical Journey and Recovery: What to Expect

    The Consultation Process: Personalized Planning

    The consultation makes the plan specific to your anatomy. Dr. Albert reviews facial proportions, skin elasticity, soft-tissue descent, asymmetry, hairline position, and the relationship among the cheek, jawline, and neck. Medical history, prior facial surgery, medications, nicotine exposure, and healing factors also require discussion. Photographs and examination help determine whether a deep plane operation, a Mini Facelift, or another facelift treatment plan is appropriate. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Ask which tissue plane the surgeon expects to enter, which retaining ligaments may require release, and how the vertical vector will adapt to your face. Request information about incision placement, anesthesia, facility arrangements, postoperative supervision, scar care, activity restrictions, and warning signs. A sound recommendation addresses your concerns without promising a particular result.

    Surgical Procedure Overview: Incisions, Dissection, and Closure

    Facelift incisions are typically designed around natural contours near the temple, ear, and hairline, with the pattern adjusted for anatomy and planned tissue movement. The surgeon elevates the skin, accesses the selected deeper plane, releases appropriate attachments, and repositions tissue upward. Skin is redraped without excessive traction, and redundant skin is managed conservatively. Layered closure supports contour and reduces strain on skin edges. Incisions may fade substantially, though scars remain permanent and are affected by skin type, tension, and healing.

    Post-Operative Recovery: A Detailed Timeline

    Recovery varies with dissection, tissue response, general health, and postoperative instructions. Early swelling, tightness, bruising, numbness, and uneven appearance can change considerably during healing. Your surgical team should provide individualized instructions rather than a generic schedule.

    Recovery phase Common considerations Patient priorities
    First several days Swelling, bruising, tightness, fatigue, and temporary numbness Follow wound-care instructions, rest, keep scheduled evaluations, and report concerning changes
    First few weeks Bruising generally settles, while firmness and altered sensation may persist Gradually resume activities only when cleared and protect healing incisions
    Following months Swelling continues to refine, scars mature, and facial sensation may normalize gradually Attend follow-up visits and allow tissues time to settle before judging the result

    Managing Swelling and Bruising: Navigating the Early Stages

    Sleep positioning, activity limits, incision care, and prescribed follow-up are central to early recovery, but instructions differ by surgeon and operation. Do not add medications, supplements, compression, or topical products without direct guidance. Contact the surgical team promptly for increasing pain, spreading redness, drainage, fever, sudden one-sided swelling, shortness of breath, or any concerning symptom. Early tightness and photographs do not represent the settled outcome.

    Long-Term Healing and Final Results

    Facial tissues mature gradually. Firmness, numbness, scar coloration, and small contour differences may improve over an extended healing period. Follow-up visits assess incision quality, nerve function, swelling, and facial balance. Aging continues after surgery, and the operation cannot prevent future changes or correct every aspect of skin quality. The appropriate recommendation matches the location of structural descent, skin condition, and your willingness to accept surgery, recovery, scarring, and uncertainty. A Mini Facelift may suit selected, localized laxity, while deeper correction requires a different assessment and operative plan.

    Frequently Asked Questions

    Is a deep plane facelift the same as a vertical facelift?

    A deep plane facelift and a vertical facelift are related terms, but they do not always describe the same operation. Deep plane refers mainly to the tissue plane and ligament release, while vertical describes the primary direction of elevation. Surgical details vary, so consultation should address the planned dissection, vector, and areas of correction.

    Is a deep plane facelift available in the USA?

    A deep plane facelift is available in the United States, including with Dr. Albert at Albert Plastic Surgery in New York City. The procedure is not a single standardized operation, and technique, anesthesia, risks, recovery, and candidacy require an individualized clinical evaluation before surgery.

    What are the cons of a deep plane facelift?

    The potential disadvantages of a deep plane facelift include a more involved operation, swelling and bruising, scarring, temporary or lasting changes in sensation, asymmetry, infection, bleeding, nerve injury, and an outcome that may not match expectations. Deep plane surgery also does not correct every wrinkle, skin-quality concern, or volume change.

    Does a deep plane facelift really last 10 years?

    A deep plane facelift may provide long-lasting improvement, but no surgeon can guarantee that results will last exactly 10 years. Continued aging, sun exposure, genetics, weight changes, skin quality, and the surgical plan affect durability. Follow-up procedures or nonsurgical treatments may be considered as facial changes continue.

    What is the best age to have a deep plane facelift?

    The best age for a deep plane facelift depends on facial aging, tissue descent, skin quality, health, and personal goals rather than a fixed number. Candidates commonly seek treatment when cheek descent, jowls, or neck laxity become bothersome. Dr. Albert determines suitability through an in-person examination and discussion of risks.

    How is a deep plane vertical facelift different from a mini facelift?

    A deep plane vertical facelift repositions selected deeper facial tissues with an upward vector, while a mini facelift generally addresses a more limited degree or location of laxity. The procedures are not automatically interchangeable. Albert Plastic Surgery offers both options, and the appropriate operation depends on anatomy, aging patterns, goals, and clinical assessment.

    What does a deep plane vertical facelift not correct?

    A deep plane vertical facelift primarily addresses descended facial tissues, cheek position, jowls, and selected jawline or neck concerns, but it does not erase every wrinkle or reverse sun damage. Fine lines, skin texture, facial volume, bone structure, and asymmetry may require separate consideration, and outcomes vary among patients.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 3, 2026 by the Albert Plastic Surgery Team
  • Deep Plane Short Scar Facelift: Technique, Candidacy, Scars, and Recovery

    Deep Plane Short Scar Facelift: Technique, Candidacy, Scars, and Recovery

    deep plane short scar facelift

    A deep plane short scar facelift combines structural release beneath the SMAS layer with shorter incisions around the ear and temple. It may improve descent in the cheek, jowl, and lower face while limiting visible scar length. Incision design, neck correction, anesthesia, recovery, and expected results depend on anatomy and a qualified surgeon’s examination.

    Key Takeaways

    • The deep plane release lifts the SMAS and underlying soft tissues together, which can create a more natural contour and longer-lasting outcome than a superficial lift.
    • Shorter incisions around the ear and temple limit visible scarring, but the exact length and placement depend on each patient's unique facial anatomy and skin laxity.
    • Good candidates typically have moderate to advanced jowling, cheek descent, or lower face sagging with adequate skin elasticity and overall health to support healing.
    • Swelling and bruising peak in the first week, and most patients can return to social activities within two weeks, with final results becoming apparent over several months.
    • Neck correction may be performed at the same time if excess fat or muscle banding is present, and this decision is made during the preoperative consultation.

    The key distinction is anatomical, not simply incision length. A limited-access operation can involve meaningful deep-plane dissection, while a superficial mini facelift may address skin and selected support tissues only. This difference helps patients evaluate recommendations, limitations, and surgical experience.

    Understanding the Deep Plane Short Scar Facelift: A Precise Approach to Facial Rejuvenation

    What Is a Deep Plane Short Scar Facelift?

    This technique uses a relatively limited incision pattern while working beneath the superficial musculoaponeurotic system, commonly called the SMAS. The surgeon releases selected facial attachments, repositions deeper soft tissue, and closes the skin with less direct tension. Intended improvements may include cheek descent, early jowling, nasolabial fullness caused by tissue migration, and reduced jawline definition.

    The Core Principle: Sub-SMAS Structural Repositioning

    The SMAS is a fibromuscular layer connected with facial muscles, fascia, and retaining structures. With age, these tissues descend and stretch. In a deep-plane operation, the surgeon works beneath the SMAS and releases selected retaining ligaments, including structures in the zygomatic and masseteric regions. This permits movement of the cheek and jowl as a connected soft-tissue unit rather than creating an isolated skin pull.

    This structural method can support a softer, proportionate appearance, but it does not stop future aging or correct every concern. Planning considers skin elasticity, tissue weight, facial proportions, skeletal support, and neck laxity. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Why “Short Scar” Matters: Incision Placement and Scar Minimization

    Short scar refers to the access route, not a smaller version of the underlying anatomy. Incisions commonly follow natural folds near the ear and extend a shorter distance behind the ear than a full facelift incision. In selected patients, temporal and postauricular portions may be limited when correction is concentrated in the cheek, jowl, and lower face. Hairline planning helps avoid distortion, step-offs, or displacement toward the temple.

    Scar visibility depends on skin behavior, incision design, closure technique, sun exposure, genetics, and healing. A shorter incision may reduce scar length but cannot make scarring invisible or eliminate widening, thickening, pigment change, or contour irregularity. Deep-plane support may reduce strong pulling force on the skin and help preserve the ear and hairline relationship.

    How This Differs from a Standard Mini Facelift and Traditional Deep Plane Lift

    A Mini Facelift generally addresses more limited laxity and focused correction, though dissection varies by patient and surgeon. A short-scar deep-plane operation is defined by work beneath the SMAS, not merely by a small incision. The choice depends on laxity, tissue descent, skin quality, and goals.

    A traditional full facelift uses longer access for greater reach toward the lateral face and neck. It may be useful for substantial skin excess, pronounced neck laxity, or platysmal banding. Limited access may suit midface and jowl descent but is not equivalent to a full operation for every anatomy.

    The Deep Plane Short Scar Facelift Technique: A Detailed Clinical Overview

    The Deep Plane Short Scar Facelift Technique: A Detailed Clinical Overview

    Anatomy Illuminated: The SMAS Layer and Its Importance

    The SMAS lies beneath subcutaneous fat and above deeper facial structures. It connects with superficial facial muscles and supports the cheek and lower face. Assessment considers the skin envelope, fat compartments, facial ligaments, parotid region, and muscle movement to determine whether limited access can provide adequate movement without excessive skin tension.

    The “Deep Plane” Dissection: Releasing and Repositioning Underlying Tissues

    After incision and exposure, dissection proceeds beneath the SMAS in selected areas. Retaining ligaments tethering the descended cheek and jowl can be released under direct visualization. The surgeon mobilizes the deeper soft-tissue layer and redirects it along a vector chosen for the patient’s anatomy. The goal is support that respects facial movement and proportion, not a fixed expression or over-tightened surface.

    Limited Incision Strategy: Navigating the Periauricular Area

    The periauricular incision follows contours around the ear. Its location is shaped by the tragus, earlobe, sideburn, hairline, and skin laxity. Limited access reduces visibility and instrument reach, so the surgeon must balance adequate release with protection of facial nerve branches, blood supply, and ear position. Incision length should provide safe, effective access rather than serve as an objective by itself.

    Structural Support: The Role of Retaining Ligament Release and Suturing

    Releasing selected zygomatic and masseteric retaining ligaments allows cheek and jowl tissues to move as a unit. Support is directed to the deeper fibro-muscular layer rather than the skin alone. Sutures may secure the SMAS or related deep fascia. StatPearls describes this layered approach as a way to limit excessive load on the skin closure, though technique and tissue response vary.

    Addressing Midface and Jowl Descent Through Limited Access

    The principal targets are often lateral cheek descent, prejowl fullness, and jowling along the mandibular border. Deep-plane mobilization may improve the cheek-to-jawline transition by repositioning existing tissue rather than creating fullness through an artificial pull. Results depend on tissue weight, ligament release, skin recoil, and lower-face or neck laxity. Limited access cannot guarantee adequate correction when aging extends beyond safely reachable areas.

    The Art of Tension-Free Skin Closure and Scar Management

    After deeper support is established, the skin is conservatively redraped and trimmed as needed. Tension-conscious closure helps preserve the ear, sideburn, and hairline contours while reducing a stretched appearance. Redness, firmness, itching, or uneven pigmentation may occur during healing. Follow the surgeon’s scar-care instructions; drainage, increasing redness, fever, severe pain, or sudden swelling requires prompt medical contact.

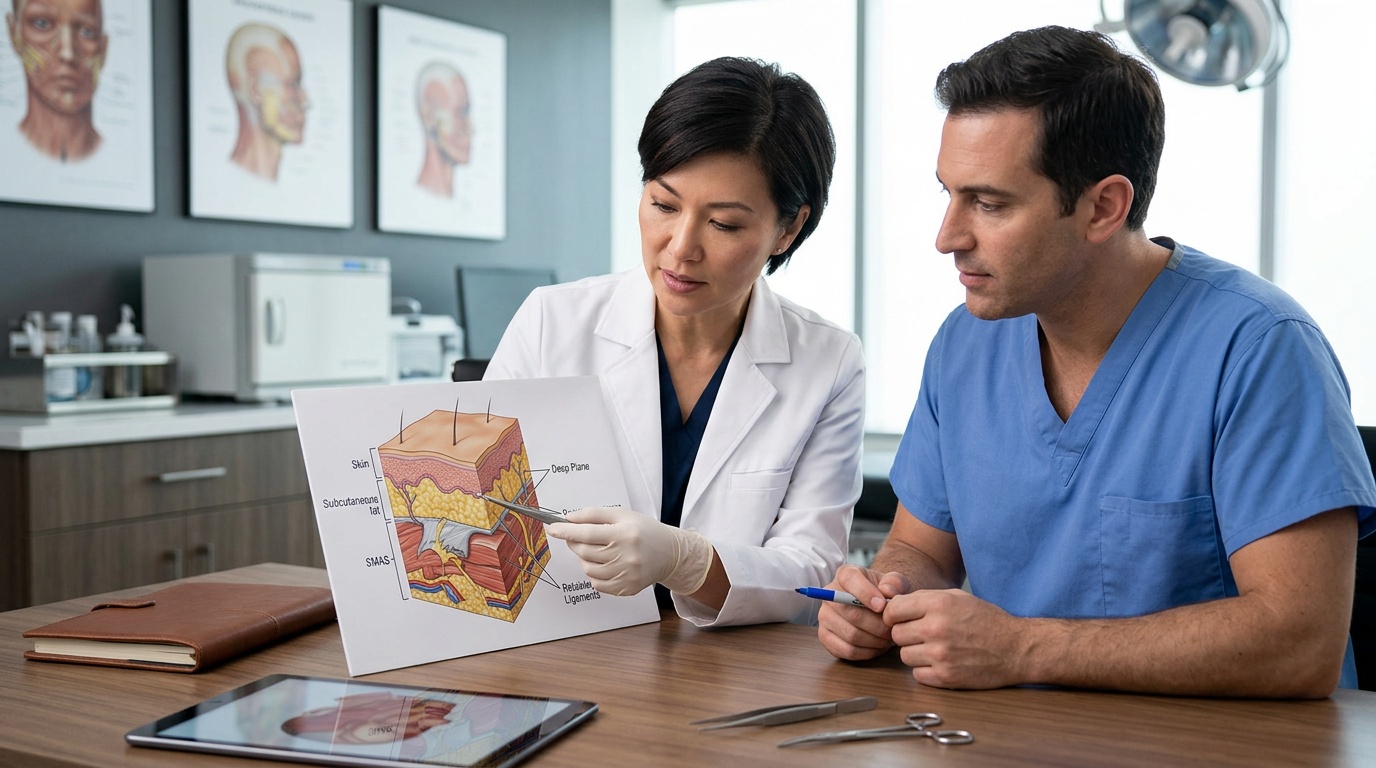
    Layered anatomy diagram explanation: From superficial to deep, the skin overlies subcutaneous fat, the SMAS and facial muscle network, deeper fascia, and underlying structures. In a deep-plane approach, the surgeon works beneath the SMAS while preserving the connection between skin and subcutaneous tissues. This allows structural repositioning through limited access, but safe dissection planes and reachable areas differ among patients.

    The deep plane short scar facelift is a technical operation, not a label based only on incision size. Planning accounts for facial anatomy, vascularity, nerve safety, tissue mobility, and the required correction. A Mini Facelift may suit limited laxity, while another patient may need broader access. An in-person consultation with a board-certified plastic surgeon is necessary.

    Candidacy and Limitations: Who Benefits Most from a Short Scar Deep Plane Facelift?

    Ideal Candidates: Characteristics for Short Scar Deep Plane Success

    A deep plane short scar facelift may suit adults with early to moderate descent concentrated in the midface, lower cheek, jowls, or jawline. Typical candidates have reasonable skin elasticity, realistic expectations, stable health, and a preference for structural repositioning rather than a skin-only pull. It may be considered when aging changes are visible but loose skin and neck laxity do not require full-facelift access.

    Candidacy cannot be determined from age or photographs alone. Assessment includes facial proportions, skin thickness, tissue weight, retaining ligaments, hairline, ear anatomy, medical history, medications, nicotine exposure, and healing factors:

    • Descent of the cheek, jowl, or lower face as the primary concern.
    • Skin that can redrape without substantial residual excess.
    • Understanding that scars remain possible, even with shorter incisions.
    • Willingness to follow surgical and postoperative instructions.
    • Acceptance that candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Midface and Jowl Focus: Strengths of the Limited Incision Approach

    Limited access can help when changes involve cheek descent, lateral midface flattening, early marionette-area heaviness, or mandibular jowling. Releasing selected zygomatic and masseteric retaining ligaments may move connected soft tissue rather than place the main corrective force on the skin. This may support a natural facial vector, though tissue response varies.

    Neck Correction: When Short Scar Is Insufficient

    A short incision does not provide unlimited reach. Significant loose neck skin, heavy lower-face tissue, submental fullness, or laxity extending behind the ear may require longer incisions and wider exposure. Patients seeking neck refinement should ask which neck structures the operation can address. A limited approach may improve the jawline while leaving neck skin or contour irregularity when aging extends beyond its access.

    Understanding Neck Laxity, Platysmal Bands, and Their Impact on Incision Choice

    Neck laxity can involve redundant skin, platysma separation or banding, reduced jawline definition, and weakened support beneath the chin. Platysmal bands may remain apparent if the plan does not reach or manage the relevant anatomy. Extended postauricular access may be more appropriate when correction continues around the side and back of the neck. Incision planning should follow the treatment area.

    Factors That May Make a Traditional Full-Incision Deep Plane Facelift More Appropriate

    A full-incision deep-plane facelift may provide broader access for substantial skin excess, advanced jowling, marked neck laxity, prominent platysmal bands, or descent across the lower face and neck. Longer access can permit controlled redraping over a wider field. The appropriate operation depends on correction required, anatomy, safety, and the surgeon’s examination.

    Planning factor Limited-incision deep-plane approach Full-incision deep-plane approach
    Primary reach Midface, cheek, jowl, and selected jawline changes Broader lateral face, jawline, and neck access
    Neck laxity May be limited when skin excess or platysmal banding is pronounced More suitable when correction extends widely through the neck
    Scar pattern Shorter periauricular or postauricular access, with individual scar risks Longer access, potentially necessary for adequate tissue reach

    Age, Skin Quality, and Lifestyle Considerations

    Age alone does not establish eligibility. Skin recoil, sun damage, collagen quality, facial volume distribution, weight stability, and tissue descent matter more than a number. Smoking or nicotine exposure, uncontrolled medical conditions, and difficulty following restrictions may increase healing and surgical concerns. An individualized facial rejuvenation plan may suit limited laxity, while broader changes may require another operation. Individual evaluation is the basis for that decision.

    Recovery, Scarring, and Realistic Expectations Post-Procedure

    The Recovery Journey: What to Expect Day-by-Day and Week-by-Week

    Recovery after a deep plane short scar facelift varies with dissection, anesthesia, tissue response, and health. During the first several days, patients typically rest with the head elevated and attend follow-up visits. Bruising and tightness may be most noticeable during the first week. By the second week, many can resume light activities, though swelling and altered sensation may remain. Healing continues for several weeks, so early appearance should not determine the final result.

    Swelling, Bruising, and Discomfort: Managing Postoperative Symptoms

    Swelling, bruising, numbness, pressure, and mild tenderness are possible, with severity varying by patient. Instructions may address head elevation, bathing, incision protection, activity limits, and medication. Do not add, stop, or change medication without medical guidance. Increasing one-sided swelling, heavy bleeding, worsening redness, fever, breathing difficulty, severe pain, or drainage requires immediate contact with the surgical team or urgent evaluation.

    Scar Maturation: Understanding the Phases of Scar Healing

    Facelift scars may appear pink, firm, or uneven early on. Over subsequent months, collagen remodeling can soften and lighten them. Genetics, pigmentation, sun exposure, incision tension, and wound healing affect maturation. Shorter access reduces scar length but does not eliminate widening, thickening, hairline displacement, pigment change, or contour irregularity around the ear and temple.

    Scar Care Protocols for Optimal Results

    Begin scar care only after the incision has closed and the surgeon approves it. Sun protection, avoiding friction, and following cleansing or topical-product instructions can support maturation. Silicone-based care may be recommended, but selection and timing belong to the treating clinician. Report separation, persistent crusting, unusual warmth, or a raised scar rather than self-treating.

    Return to Social Activities and Work

    Return to work depends on bruising, swelling, job demands, commute, and comfort with public visibility. Desk work may resume before strenuous activity, while heavy lifting and movements that increase facial pressure generally remain restricted until clearance. Social readiness may occur later than basic mobility because subtle swelling can persist after bruising fades. The operating surgeon should provide a personal timeline.

    Longevity of Results: How Long Does This Facelift Typically Last?

    Structural improvement is long lasting but not permanent. Research describes deep-plane facelift durability in the approximate range of 10 to 15 years. This is an average reference, not a promise. Genetics, ultraviolet exposure, weight change, skin quality, and ongoing aging affect duration.

    Understanding Realistic Outcomes: Avoiding Unnatural Appearances

    The objective is a refreshed, proportionate appearance with preserved expression, not a frozen or pulled look. Natural results depend on appropriate vectors, conservative skin redraping, respect for facial anatomy, and realistic goals. Surgery cannot erase every line or restore youthful tissue permanently. An in-person examination is necessary before forming expectations about visible change.

    Evaluating Your Options: Consultation, Costs, and Choosing Your Surgeon

    Evaluating Your Options: Consultation, Costs, and Choosing Your Surgeon

    What to Discuss During Your Consultation: Key Questions to Ask

    Ask which anatomical concerns the operation addresses, where incisions will sit, how neck laxity will be evaluated, what restrictions apply, and which risks relate to your health. Request an explanation of the surgical plane, anesthesia plan, follow-up schedule, scar expectations, and circumstances requiring additional care. Ask whether the plan addresses midface and jowl descent, neck correction, or both.

    Understanding the Factors Influencing Procedure Cost

    Pricing may reflect surgeon expertise, facility fees, anesthesia, location, preoperative assessment, postoperative visits, garments or supplies, and dissection complexity. A limited incision does not automatically mean a minor operation or predictable fee. Request an itemized estimate and clarify included services, separate charges, and handling of unexpected medical needs.

    Transparent Pricing: What the Procedure May Entail

    The cost of a deep plane short scar facelift cannot responsibly be quoted from a description alone. Incision design, dissection extent, neck involvement, anesthesia, facility selection, and safety planning influence the estimate. A written proposal should follow examination and is not a guarantee of outcome or final recovery.

    Why Board Certification and Experience Matter in Facial Surgery

    Look for a surgeon certified by the American Board of Plastic Surgery with facial-anatomy training, operative judgment, complication-management skills, and continuity of care. Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery is certified by the American Board of Plastic Surgery and a Fellow of the American College of Surgeons. He completed plastic surgery residency and chief residency at the University of Massachusetts Medical School, followed by aesthetic plastic surgery fellowship training at MEETH.

    Dr. Mark G. Albert’s Approach to Individualized Care

    Dr. Albert’s planning at Albert Plastic Surgery centers on facial structure, skin behavior, neck anatomy, personal goals, and patient safety. Dr. Albert is Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Next Steps: Scheduling Your Personalized Consultation

    A consultation is the appropriate next step for careful assessment rather than a predetermined operation. Bring your medical history, medication list, prior surgical information, and questions about scars, recovery, cost, and neck correction. Discuss whether the Nanolift™ facial rejuvenation option or a deep-plane approach fits your anatomy and goals.

    Frequently Asked Questions

    What is the downside of a deep plane facelift?

    The main downsides of a deep plane facelift include surgical risks, a more demanding dissection, limited correction of significant neck laxity, visible or changing scars, and results that vary by anatomy and healing. Facial nerve injury, bleeding, infection, contour irregularity, hairline or ear changes, and the possibility of revision should be discussed during consultation.

    How much younger do you look after a deep plane facelift?

    A deep plane facelift can make the face appear more rested and may reduce cheek descent, jowling, and lower-face laxity, but it cannot reliably be measured as a specific number of years younger. Age perception varies with facial structure, skin quality, neck changes, treatment selection, healing, and natural aging after surgery.

    Is a deep plane facelift available in the USA?

    A deep plane facelift is available in the United States, including through qualified facial plastic and plastic surgeons who perform the procedure in appropriate settings. The technique, incision pattern, anesthesia plan, risks, recovery, and need for neck correction require an examination and discussion with a board-certified surgeon.

    What does a deep plane facelift look like after 10 years?

    A deep plane facelift may continue to provide a more supported cheek, jawline, and lower face after 10 years, but it does not stop aging. Skin, soft tissue, sun exposure, weight changes, genetics, and medical factors influence long-term appearance, and some patients may later consider non-surgical care or additional surgery.

    What is the most regretted cosmetic surgery?

    No single cosmetic surgery is universally the most regretted, because dissatisfaction often reflects mismatched expectations, complications, inadequate planning, or a result that does not fit the patient’s anatomy. Deep plane short scar facelift decisions should include realistic goals, limitations, recovery, risks, alternatives, and the possibility that further treatment may be needed.

    Who may be a candidate for a deep plane short scar facelift?

    A deep plane short scar facelift may suit patients with cheek descent, early jowling, or lower-face laxity who may not need the access of a full facelift. Candidacy depends on skin elasticity, tissue weight, neck laxity, facial proportions, skeletal support, health, and goals, all of which require individualized clinical assessment.

    How is a deep plane short scar facelift different from a mini facelift?

    A deep plane short scar facelift is defined by repositioning selected tissues beneath the SMAS, while a mini facelift may use more limited dissection focused on skin and selected support tissues. Shorter incisions do not determine the anatomic plane, and meaningful neck laxity or skin excess may require a broader operation.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 3, 2026 by the Albert Plastic Surgery Team
  • The Complete Guide to Deep Plane Lower Facelift Cost

    The Complete Guide to Deep Plane Lower Facelift Cost

    deep plane lower facelift cost

    The deep plane lower facelift cost depends on the scope of surgery, the surgeon’s professional fee, anesthesia, and the accredited operating facility. A meaningful estimate cannot be based on a procedure name alone. Two patients may receive different quotes because one plan addresses only the lower face, while another includes broader tissue release, a longer operating time, or treatment of the neck. Ask for a written estimate that identifies every included charge.

    Key Takeaways

    • The cost of a deep plane lower facelift varies because the total fee includes the surgeon's professional charge, anesthesia, and the accredited operating facility, each of which can differ by patient.
    • Two patients may receive different quotes for the same procedure name when one plan requires only lower face work and the other includes broader tissue release, extended operating time, or neck treatment.
    • Ask for a written estimate that itemizes every included charge, because the final price depends on the specific scope of surgery rather than the procedure name alone.
    • Do not assume a single price based on the term "deep plane lower facelift," as the extent of dissection and the surgeon's technique directly influence the operating time and the final cost.

    Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery individualizes facelift planning around facial anatomy, skin quality, tissue descent, jawline definition, and the appearance you want to preserve. Dr. Albert is certified by the American Board of Plastic Surgery and a Fellow of the American College of Surgeons. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    What is deep plane lower facelift cost?

    The term refers to the anticipated expense of a lower facelift performed with a deep-plane approach. It is not a universal fee or a standardized package. The surgeon’s fee generally reflects consultation, surgical planning, technical complexity, and postoperative care. Separate charges may include anesthesia and the operating-room or facility fee. Before scheduling, confirm whether the estimate includes preoperative evaluation, anesthesia professionals, facility services, surgical garments or supplies, follow-up visits, and care for an unexpected concern.

    A deep-plane facelift involves work beneath the superficial musculoaponeurotic system, often described as the SMAS, with attention to facial retaining ligaments and descended cheek or jowl tissues. The exact dissection and surgical boundaries vary by patient. A lower facelift may focus on the jawline, jowls, lower cheeks, and upper neck, but “lower facelift” does not automatically mean that the neck is included. The operative plan should state whether the neck is part of the treatment area and how that affects the estimate. Patients can review the practice’s deep-plane facelift approach when preparing questions for consultation.

    Cosmetic facelift surgery is generally elective and is typically not covered by health insurance. Coverage questions belong with your insurer, particularly if a separate medical concern exists. Do not select a surgeon based on the lowest advertised figure. A qualified consultation should explain the anatomy being addressed, the planned incision placement, anesthesia arrangements, facility setting, likely recovery process, limitations, and material risks such as bleeding, infection, scarring, nerve changes, contour irregularity, asymmetry, hairline changes, and the possibility of revision surgery.

    Benefits of deep plane lower facelift cost

    Benefits of deep plane lower facelift cost

    When patients ask about the benefits associated with the deep plane lower facelift cost, the more useful question is what the planned surgery is intended to accomplish. A properly selected lower facelift may improve visible jowling, laxity along the mandibular border, lower-cheek descent, and selected signs of upper-neck looseness. By repositioning deeper facial tissues rather than relying only on skin tension, the surgeon can plan a result that respects facial proportions and preserves a recognizable appearance. The goal is not to create a frozen, pulled, or unfamiliar look.

    The deep-plane approach may be considered when the surgeon determines that deeper tissue descent contributes substantially to the patient’s concern. It is not automatically the best technique for every face. Skin elasticity, soft-tissue volume, facial width, skeletal structure, prior surgery, medical history, tobacco exposure, and healing capacity all influence technique selection. A patient whose primary concern involves an issue outside the lower face may not receive a satisfactory answer from a lower facelift alone. A consultation should distinguish true tissue descent from concerns that a facelift cannot correct.

    Key insight: Price should be evaluated alongside surgical scope and continuity of care. A lower quote may exclude anesthesia, facility charges, or postoperative services. A higher quote may reflect a longer operation, a broader treatment area, or a different level of facility and anesthesia support. Request an itemized estimate and ask which elements are fixed, which may change, and who will explain additional charges before surgery.

    Some patients may be better suited to a more limited approach. Albert Plastic Surgery maintains a dedicated live service page for Mini Facelift. A Mini Facelift may be discussed when the degree and location of laxity support a smaller surgical plan, although only an in-person examination can determine whether that approach is appropriate. The benefit of careful selection is not a promised outcome. It is a treatment plan matched to anatomy, expectations, safety considerations, and the areas the patient actually wishes to address.

    How to Choose deep plane lower facelift cost

    Choosing a surgeon based on deep plane lower facelift cost requires more than comparing a single number. Begin by defining the treatment area and the concern you want addressed. A lower facelift may involve the jowls, lower cheeks, jawline, or upper neck, while a deep-plane technique describes how the surgeon works with deeper facial tissues. Those terms do not create a standardized package. Ask whether the proposed plan includes the neck, which anatomic layers require treatment, where incisions will be placed, and why the selected approach fits your facial structure.

    Request a written, itemized estimate before making a scheduling decision. The document should identify the surgeon’s professional fee, anesthesia services, operating-room or facility charges, preoperative medical evaluation, supplies, postoperative appointments, and any prescribed recovery materials. Ask whether the anesthesia professional is qualified for the planned surgery and whether the facility is accredited by a recognized accrediting organization. A quote that omits facility or anesthesia charges may appear lower without representing the eventual total. Also ask how the practice handles an unexpected change in the operative plan or a postoperative concern, including which services may create additional fees.

    Credentials and surgical judgment deserve the same attention as financial details. Verify that the surgeon is certified by the American Board of Plastic Surgery through the appropriate official certification source, rather than relying only on a general statement that a physician is “board certified.” Review the surgeon’s education, current hospital or facility privileges when relevant, experience with facelift anatomy, and approach to informed consent. Dr. Albert is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. During consultation, ask to discuss tissue descent, skin elasticity, facial asymmetry, scar placement, nerve anatomy, healing factors, and the limits of surgery.

    Use the consultation to evaluate whether your expectations align with what a lower facelift can accomplish. A natural-looking result depends on proportion, appropriate tissue repositioning, and preservation of recognizable facial features. Surgery may not address every concern involving facial appearance, and a lower facelift may be unsuitable when the primary issue lies outside its treatment boundaries. Share your medical history, medications, allergies, nicotine exposure, previous facial surgery, and any condition that could affect anesthesia or wound healing. The surgeon should explain possible bleeding, infection, scarring, temporary or persistent nerve changes, contour irregularity, asymmetry, hairline changes, unfavorable healing, revision surgery, and the expected recovery process. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Finally, compare estimates only after confirming that the surgical scope is genuinely comparable. One plan may involve limited lower-face tightening, while another may include deeper tissue release, broader dissection, or treatment extending into the neck. Ask who will provide follow-up care, how urgent questions are managed, and whether the practice maintains continuity from consultation through healing. Cosmetic facelift surgery is generally elective and typically is not covered by health insurance, though coverage questions belong with your insurer. A qualified in-person consultation is the appropriate setting for determining whether the proposed operation, facility, anesthesia plan, and total expense suit your needs. Patients considering broader treatment can also review the practice’s facelift surgery options before comparing estimates.

    Frequently Asked Questions

    How much does a deep-plane lower facelift cost?

    There is no single price that applies to every patient. The total usually reflects the surgeon’s professional fee, anesthesia services, and operating-room or facility charges. Surgical scope also matters. A plan limited to the lower face may differ from one that includes the upper neck, more extensive tissue release, or a longer operating time. Request an itemized estimate during consultation, and confirm which services, supplies, follow-up visits, and facility expenses are included.

    Why can two surgeons provide very different quotes?

    Quotes may describe different operations despite using similar terminology. Surgeons may recommend different treatment boundaries, incision patterns, dissection methods, anesthesia arrangements, or facility settings. Their postoperative care policies may also differ. A meaningful comparison requires reviewing the proposed anatomy, surgical technique, anesthesia professional, facility, follow-up plan, and payment terms rather than comparing advertised numbers alone.

    Does the quoted price include anesthesia and the operating facility?

    Not always. Some practices present a combined estimate, while others list the surgeon’s fee separately from anesthesia and facility charges. Ask for written confirmation of every included component before scheduling. You may also ask whether the facility is accredited by a recognized organization and which qualified anesthesia professional will participate in surgery. These questions support informed financial and safety planning.

    Is a deep-plane lower facelift less expensive than a full facelift?

    Not necessarily. A lower facelift may cover a smaller facial region, yet the price depends on operative complexity, time, facility services, anesthesia, and the individual treatment plan. The word “deep-plane” describes an anatomic approach, not a fixed fee. Only estimates with comparable surgical scope can be evaluated fairly.

    Does a lower facelift include the neck?

    A lower facelift does not automatically include the neck. Some plans address the jawline, jowls, and lower cheeks, while others extend into the upper neck. Ask the surgeon to identify the exact treatment boundaries and explain how neck treatment changes the surgical plan, recovery expectations, risks, and cost. Candidacy and technique require an in-person medical assessment.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 2, 2026 by the Albert Plastic Surgery Team
  • Deep Plane vs SMAS Facelift: What's Best?

    Deep Plane vs SMAS Facelift: What's Best?

    deep plane facelift vs smas

    When considering deep plane facelift vs smas, the central question is not which technique is universally better. The decision depends on facial anatomy, skin laxity, soft-tissue descent, neck changes, desired degree of correction, and the surgeon’s assessment during consultation. Both operations are designed to create a refreshed, proportionate appearance without relying on excessive skin tension.

    Key Takeaways

    • The choice between a deep plane and SMAS facelift depends on how much your facial tissues have descended and how your neck has changed, not on one method being superior for everyone.
    • A thorough consultation with your surgeon will determine which technique best addresses your specific degree of skin laxity and soft tissue sagging.
    • Both procedures prioritize repositioning deeper facial layers to achieve a natural, balanced look rather than relying on pulling the skin tight.
    • Your facial anatomy and the amount of correction you desire are the true factors that guide the recommendation for either a deep plane or SMAS facelift.

    Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery is certified by the American Board of Plastic Surgery and a Fellow of the American College of Surgeons. His approach begins with careful evaluation of the lower face, jawline, cheeks, neck, skin quality, facial proportions, and personal goals. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    What is deep plane facelift vs smas?

    A SMAS facelift works with the superficial musculoaponeurotic system, a supportive layer beneath the facial skin. Depending on the surgical plan, the surgeon may reposition, tighten, or selectively release this layer before redraping the skin. A deep plane facelift releases specific retaining ligaments and lifts the skin and deeper soft tissue as a connected unit. This can address descent through the cheeks, jowls, jawline, and selected areas of the neck while reducing dependence on skin traction.

    The technical distinction matters, but it does not determine the result by itself. A natural appearance depends on sound anatomy, conservative tissue handling, appropriate vector selection, incision placement, skin redraping, and the surgeon’s judgment regarding the limits of correction. Deep plane surgery is not automatically superior, and a SMAS facelift is not a single standardized operation. Both techniques have variations, and the most appropriate plan may differ between patients with similar concerns.

    A 2025 systematic review and one-arm meta-analysis indexed in PubMed evaluated 21 studies involving 2,896 patients. The pooled reports showed patient satisfaction of 94.4% for deep plane procedures and 87.8% for SMAS procedures, with reported overall complication rates of 17.2% and 10.3%, respectively. These findings represent observational evidence with differences in study design, patient selection, surgeon technique, and complication reporting. They do not prove that one approach is safer or produces better results for every individual.

    Benefits of deep plane facelift vs smas

    Benefits of deep plane facelift vs smas

    The potential benefit of a deep plane facelift is its ability to reposition deeper facial tissues rather than relying primarily on skin tightening. This may be useful when midface descent, pronounced jowls, or a heavier lower face are central concerns. A SMAS facelift can also provide meaningful improvement in the lower face and jawline, with the exact effect shaped by whether the SMAS is tightened, folded, repositioned, or released. Neither operation can recreate youthful anatomy perfectly, remove every line, or stop future aging.

    Key insight: A natural-looking facelift is measured by balanced facial movement, a defined but not harsh jawline, a smooth transition from the face to the neck, and preservation of personal identity. The technique should serve the anatomy, not replace individualized planning.

    Patients often ask whether a deep plane operation lasts longer. Some published sources describe longer average duration for deep plane results, while other reports emphasize that longevity varies with age, genetics, sun exposure, skin elasticity, weight changes, and surgical design. It is more accurate to discuss durability as a range of possibilities rather than a promised timeline. Published estimates for SMAS facelift recovery commonly center on about two weeks, while deep plane recovery is often described as approximately two to three weeks. These are general estimates, not individualized clearance dates.

    Cost also reflects more than the named technique. A quoted SMAS facelift cost or deep plane mini facelift cost may include different surgeon fees, anesthesia, facility charges, garments, follow-up care, and geographic expenses. International prices may use different inclusions and currencies, so direct comparisons can mislead. Patients should request a written explanation of the surgical plan and fees rather than selecting an operation based on price alone.

    A Mini Facelift may be considered when laxity is more limited and the desired correction is appropriately focused. Mini Facelift is directly within the client-directed facelift scope. It is not simply a smaller version of every other facelift, and its suitability depends on the distribution of skin laxity, jowling, facial descent, and neck changes. A consultation is needed to determine whether its scope matches the patient’s goals.

    How to Choose deep plane facelift vs smas

    Choosing between deep plane facelift vs smas begins with the pattern of facial aging rather than a preference for a technical label. During consultation, Dr. Albert evaluates skin elasticity, cheek descent, jowls, jawline definition, neck laxity, facial fullness, tissue thickness, and overall proportions. He also considers whether your priority is a focused lower-face correction or broader repositioning through the midface and neck. Photographs, examination, medical history, prior surgery, medications, smoking status, and your recovery expectations all contribute to an individualized plan.

    A deep plane approach may be considered when descended cheek tissues, prominent jowls, or lower-face heaviness require movement of deeper structures with less reliance on skin traction. A SMAS facelift may be appropriate when the primary concerns involve lower-face laxity, jawline irregularity, or selected neck changes that can be addressed through a carefully designed SMAS operation. The distinction between deep plane facelift vs smas is not a reliable way to predict which patient will obtain the most natural result. Incision design, tissue handling, vector selection, skin redraping, and surgical judgment remain central.

    Ask during consultation which anatomic findings support the proposed technique and which concerns it may not fully address. A facelift can improve lax skin, jowling, facial descent, and some neck laxity, but it does not erase every wrinkle, correct all changes in skin texture, or prevent future aging. Patients concerned about their front view should ask how the plan addresses cheek position, facial width, nasolabial transition, jawline contour, and neck-to-face balance, rather than evaluating the operation only through a side profile.

    Price should be reviewed only after the surgical scope is clear. A quoted SMAS facelift cost may differ according to surgeon experience, operating facility, anesthesia, geographic location, complexity, follow-up, and included services. The same issue applies when researching a deep plane mini facelift cost: a limited operation is not interchangeable with a full facelift, and a lower fee may reflect a narrower scope rather than better value. Request a written estimate that identifies professional fees, facility charges, anesthesia, postoperative visits, and any planned revisions or additional care.

    Recovery planning also belongs in the decision. General published estimates often describe roughly two weeks for SMAS recovery and approximately two to three weeks for deep plane recovery, though swelling, bruising, numbness, incision healing, activity restrictions, and return to work vary by patient. Your surgeon should provide specific instructions for wound care, sleeping position, exercise, driving, travel, and follow-up. Do not use a generic recovery calendar as personal medical clearance.

    The Mini Facelift may suit selected patients whose laxity and jowling are limited and whose goals call for a more focused correction. Mini Facelift is directly within the client-directed facelift scope. Its suitability cannot be determined by age alone, and it may not provide the desired correction when descent extends through the cheeks, jawline, or neck. A qualified surgeon should explain the expected scope, visible limitations, material risks, anesthesia plan, and follow-up requirements before you decide.

    Frequently Asked Questions

    Is a deep plane facelift better than a SMAS facelift?

    Neither technique is universally better. The appropriate operation depends on the location and degree of tissue descent, skin elasticity, jawline definition, neck laxity, facial proportions, medical history, and the result you hope to achieve. A deep plane facelift may be considered when deeper cheek and lower-face tissues have descended. A SMAS facelift may suit a different pattern of laxity. The surgeon’s examination and operative plan matter more than selecting a technique by name alone.

    Which approach gives the most natural-looking result?

    A natural-looking result depends on conservative planning, accurate tissue repositioning, appropriate vector selection, careful skin redraping, and respect for individual anatomy. Neither a deep plane facelift nor a SMAS facelift guarantees a particular appearance. During consultation, ask how the proposed plan will preserve facial identity, movement, jawline proportion, and the transition between the face and neck. It is also reasonable to ask which visible concerns may remain after surgery.

    Which option is better for jowls, the jawline, neck, or midface?

    The answer depends on the source of the concern. Jowling and jawline laxity may be addressed through several facelift designs. Midface descent can call for a plan that repositions cheek tissues, while neck improvement depends on the pattern of laxity and the relationship between the lower face and neck. A facelift cannot correct every skin-quality change or eliminate all lines. An in-person examination is necessary to identify which structures contribute to the appearance and what degree of correction is realistic.

    Does a deep plane facelift last longer than a SMAS facelift?

    Published discussions sometimes describe longer-lasting improvement with deep plane surgery, but durability varies substantially among patients. Age, genetics, sun exposure, skin quality, weight changes, smoking, tissue characteristics, and surgical design can affect how the face changes over time. Longevity should be discussed as an expectation with uncertainty, not a fixed promise. Both procedures address existing descent while the natural aging process continues.

    When should I seek an in-person facelift consultation?

    Seek consultation when facial laxity, jowls, neck changes, or midface descent concern you and you want to understand the available facelift plan. Bring questions about candidacy, anesthesia, incisions, recovery, complications, follow-up, and limitations. Dr. Albert is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. A consultation does not obligate you to undergo surgery. It provides an opportunity to review your anatomy and make an informed decision.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 2, 2026 by the Albert Plastic Surgery Team
  • Deep Plane vs Regular Facelift: What's Best?

    Deep Plane vs Regular Facelift: What's Best?

    deep plane facelift vs regular facelift

    When patients search for deep plane facelift vs regular facelift, they are usually asking whether the deeper operation produces a more natural or longer-lasting result. The answer depends on facial anatomy, skin laxity, cheek position, jowling, neck changes, prior surgery, and the surgeon’s operative plan. “Regular facelift” is not a precise technical term, so the details should be confirmed during consultation.

    Key Takeaways

    • Deep plane facelifts target deeper facial layers to reposition sagging cheeks and jowls, often producing a more natural appearance than superficial techniques.
    • The term "regular facelift" is not a standard medical description, so patients should ask their surgeon for the specific technique and tissue layers involved.
    • Your facial anatomy, degree of skin laxity, and prior surgeries determine whether a deep plane or more superficial lift will give you the best outcome.
    • A thorough consultation is essential to match the surgical plan with your unique aging patterns in the cheeks, jawline, and neck.

    Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery evaluates the facial layers that require correction rather than selecting a technique by name alone. As a board-certified plastic surgeon and Fellow of the American College of Surgeons, he discusses what each approach can address, what it cannot change, and how healing may affect the appearance during the early postoperative period.

    What is deep plane facelift vs regular facelift?

    A deep plane facelift releases and repositions selected facial tissues beneath the superficial musculoaponeurotic system, commonly called the SMAS. This deeper mobilization may allow the cheek and midface tissues to move together with the lower face. A traditional or “regular” facelift may involve tightening the SMAS, repositioning it, or working primarily with the skin and supporting layers. Since terminology varies among surgeons, the name alone does not establish the exact operation.

    The distinction matters because facial aging does not occur in one layer. Skin may lose elasticity, fat compartments may shift, retaining ligaments may become less supportive, and the jawline or neck may develop laxity. A deep plane approach can be useful for selected patients with midface descent, prominent nasolabial folds, jowls, or broader tissue movement needs. A SMAS-based facelift may be appropriate when the main concerns involve lower-face laxity, jawline definition, or neck skin. Neither method is automatically better for every patient.

    Key insight: A natural result depends on accurate assessment, conservative tissue handling, appropriate vector selection, and realistic expectations. A photograph taken several days after surgery may show swelling, bruising, dressings, lighting effects, or camera adjustments. It should not be treated as a final representation of healing.

    Benefits of deep plane facelift vs regular facelift

    Benefits of deep plane facelift vs regular facelift

    The potential benefit of a deep plane facelift is coordinated movement of deeper facial tissues rather than relying on skin tension alone. In a suitable patient, this may improve the transition between the lower eyelid and cheek, soften descent through the midface, reduce jowling, and restore a more continuous contour from the cheek toward the jawline. The technique may also reduce the chance that the skin carries the full lifting force, which can support a less tight-looking appearance. These effects depend on anatomy, surgical judgment, healing, and the amount of correction required.

    A traditional facelift, including a SMAS facelift, can offer meaningful correction when laxity is concentrated around the lower face, jawline, and neck. It may provide a carefully controlled lift without the deeper dissection required in a deep plane operation. For some patients, that approach may represent a more suitable balance between goals, anatomy, operative details, and recovery considerations. A Mini Facelift may also be considered for carefully selected patients with more limited lower-face laxity, although candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    In considering deep plane facelift vs regular facelift, patients should look beyond claims about permanence or a fixed recovery schedule. Every facelift involves incisions, swelling, bruising, temporary numbness, scar maturation, and risks such as bleeding, infection, unfavorable scarring, nerve-related weakness, asymmetry, skin healing problems, and the possibility of revision. Aging continues after surgery, and no technique can stop future changes. The recommended operation should reflect the patient’s facial structure and priorities, not a promotional label. At Albert Plastic Surgery, a Mini Facelift is discussed only when its more limited scope corresponds with the patient’s needs.

    How to Choose deep plane facelift vs regular facelift

    Choosing a facelift technique should begin with the facial changes you want addressed, not with a procedure label. During consultation, your surgeon should assess skin elasticity, cheek descent, nasolabial folds, jowls, jawline definition, neck laxity, facial asymmetry, prior surgery, and overall health. Ask which anatomical layers require repositioning, whether the plan involves the SMAS, and how the proposed operation addresses your specific concerns. Terminology varies among surgeons, so “deep plane,” “SMAS,” and “regular facelift” should be accompanied by a clear explanation of the actual surgical steps.

    Patients concerned about the cheeks and midface may wish to ask whether the planned operation provides adequate mobilization of those tissues. Patients whose primary concerns involve jowling, a soft jawline, or neck laxity should ask how the lower face and neck will be treated. A deeper approach is not automatically the better choice. The appropriate plan depends on tissue position, skin quality, facial proportions, the degree of laxity, and the surgeon’s experience with the proposed dissection. A carefully performed SMAS-based facelift may be a sound choice for one patient, while another may require a different level of tissue release.

    Review the surgeon’s credentials, hospital privileges when applicable, operative setting, anesthesia plan, follow-up process, and approach to complications. Dr. Albert is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. During an evaluation at Albert Plastic Surgery, ask to see results at a mature stage of healing rather than relying on a heavily edited image or a photograph labeled “seven days postoperative.” Early swelling, bruising, numbness, temporary firmness, and uneven healing can substantially alter appearance before tissues settle.

    Which questions support an informed decision?

    Bring a written list to your consultation. Useful questions include: Which facial structures are causing my concerns? What changes can this operation reasonably provide? What limitations should I expect? Where will incisions be placed, and how do scars typically mature? What are the risks of bleeding, infection, nerve-related weakness, skin-healing problems, asymmetry, contour irregularity, and revision? Ask how follow-up is organized and which symptoms require prompt contact with the surgical team.

    A Mini Facelift may be discussed when laxity is more limited and concentrated in the lower face. Its smaller scope does not make it appropriate for everyone, and it should not be selected solely because the name suggests an easier experience. A Mini Facelift may not address substantial midface descent, marked neck laxity, or extensive skin excess. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment. The safest decision is one based on an in-person examination, transparent planning, and realistic expectations rather than a promised duration, fixed recovery schedule, or promotional photograph.

    Frequently Asked Questions

    Is a deep plane facelift better than a regular facelift?

    Not automatically. A deep plane facelift may be appropriate when the treatment plan requires movement of deeper cheek and midface tissues. A SMAS-based or traditional facelift may be well suited to patients whose principal concerns involve the lower face, jawline, or neck. The appropriate operation depends on anatomy, skin elasticity, tissue descent, medical history, and the surgeon’s assessment. A consultation should explain why a specific technique fits your facial structure and what limitations remain.

    Is a regular facelift the same as a SMAS facelift?

    “Regular facelift” is an informal phrase rather than a standardized technical description. Some surgeons use it to describe a traditional facelift involving the SMAS, while others may use different methods involving the skin and deeper supporting layers. Ask the surgeon to describe the planned dissection, tissue repositioning, incision pattern, anesthesia, and expected recovery. The procedure name alone does not provide enough information to compare surgical plans.

    Which facelift addresses the midface and cheeks?

    A deep plane approach can provide access to selected midface and cheek tissues, which may make it useful for certain patterns of cheek descent or flattening. This does not mean that every patient with cheek changes requires a deep plane operation. Facial proportions, ligament release, tissue quality, and the intended vector of movement all matter. During consultation, ask whether the proposed technique addresses the cheek area directly and how the surgeon distinguishes swelling from the eventual contour.

    Which facelift is better for jowls, a weak jawline, or neck laxity?

    Both a deep plane facelift and a SMAS-based facelift may address jowling or reduced jawline definition in selected patients. Neck laxity and excess skin require a plan tailored to the degree and location of those changes. A Mini Facelift may be considered when lower-face laxity is limited, but it is not designed for every pattern of aging. A Mini Facelift should be chosen only after an individualized examination.

    When should facelift results be judged?

    Early photographs can be misleading because swelling, bruising, numbness, firmness, lighting, makeup, and camera angle affect appearance. A “seven-day postoperative” image is not necessarily a final result. Healing and scar maturation continue over time, with the pace varying by patient and operation. Follow your surgeon’s specific instructions and contact the surgical team promptly if you develop concerning symptoms. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 2, 2026 by the Albert Plastic Surgery Team
  • The Complete Guide to Deep Plane Facelift vs Mini Facelift

    The Complete Guide to Deep Plane Facelift vs Mini Facelift

    deep plane facelift vs mini facelift

    Choosing between a deep plane facelift vs mini facelift begins with understanding what each operation is designed to change. A deep plane approach addresses deeper facial support and may be considered when aging affects the cheeks, lower face, jawline, and neck. A Mini Facelift generally involves a more limited lift for selected patients with earlier or more localized laxity. The appropriate operation depends on facial anatomy, skin quality, tissue descent, health history, and the result you hope to achieve.

    Key Takeaways

    • The deep plane facelift works beneath the muscle layer to reposition deeper facial support, while the mini facelift lifts more superficial tissue through a shorter approach.
    • Patients whose aging affects the cheeks, lower face, jawline, and neck together may benefit from the deeper, more comprehensive correction.
    • A mini facelift can suit patients with early or localized laxity who want meaningful improvement with a more limited procedure.
    • Candidacy depends on facial anatomy, skin quality, the degree of tissue descent, health history, and the outcome you hope to achieve.
    • A personal consultation with a board-certified plastic surgeon remains the most reliable way to determine which operation matches your anatomy and goals.

    This educational guide is written by Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery, certified by the American Board of Plastic Surgery and a Fellow of the American College of Surgeons. Medical review: Dr. Mark G. Albert, reviewed February 2025. Online information cannot replace an examination and consultation with a qualified plastic surgeon.

    What is deep plane facelift vs mini facelift?

    A deep plane facelift releases and repositions facial tissues beneath the superficial musculoaponeurotic system, commonly called the SMAS. This deeper dissection can address descent through the midface and lower face, with planning that may include the jawline and neck when those areas require treatment. The goal is not to pull the skin tightly, but to restore the position of underlying facial tissues while allowing the skin to rest over the revised contours.

    A Mini Facelift is typically more limited in incision pattern, tissue elevation, and treatment area. It may suit a person with mild to moderate skin laxity, early jowling, or a small amount of lower-face descent. The term “mini” is not a standardized measurement. Surgeons may use it to describe different operations, so the planned anatomy, technique, anesthesia, facility, and follow-up deserve more attention than the label alone.

    Consideration Deep plane facelift Mini Facelift
    Typical treatment focus Deeper support and broader facial descent More localized lower-face laxity
    Potential facial areas Midface, cheeks, lower face, jawline, and selected neck concerns Often the jawline and lower face, depending on the surgical plan
    Patient selection More advanced or distributed tissue descent may be present Earlier aging changes and adequate skin elasticity may be present
    Extent of surgery Generally more comprehensive Generally more limited

    Benefits of deep plane facelift vs mini facelift

    Benefits of deep plane facelift vs mini facelift

    The potential benefit of a deep plane facelift is its ability to reposition deeper facial structures rather than relying primarily on skin tension. This may support a softer transition through the cheek, lower face, and jawline when those tissues have descended together. A properly planned operation can help avoid an overly pulled appearance, though no technique can guarantee a particular aesthetic result. A deep plane approach may be less suitable when a patient’s concerns are limited, when medical factors increase risk, or when the proposed scope exceeds the person’s goals.

    The benefit of a Mini Facelift is proportionate treatment for carefully selected patients. A more limited operation may address early jowls or mild laxity without undertaking a broader facial dissection. It can be a reasonable consideration when the midface remains well positioned and the principal concern is confined to the lower face. It may not provide the same correction when cheek descent, substantial neck laxity, pronounced skin excess, or wider facial aging is present. The Mini Facelift should be understood as a specific surgical plan, not simply a shorter version of every comprehensive facelift.

    Patients often ask whether one approach is better. The answer depends on the anatomy being treated, the surgeon’s examination, realistic expectations, and the balance between correction and surgical extent. Neither operation stops future aging, and longevity varies with genetics, skin elasticity, weight changes, sun exposure, smoking, and postoperative care. Complications can include bleeding, infection, delayed wound healing, unfavorable scarring, numbness, hairline changes, facial nerve injury, asymmetry, contour irregularity, and the possibility of revision. The risk profile varies with the technique and the individual.

    Cost comparisons also require care. A deep plane mini facelift cost discussion may involve different definitions of “mini,” surgeon fees, anesthesia, operating-room charges, facility standards, garments, medications, and postoperative visits. A quote with a lower price may not represent the same operation or level of care. During consultation, ask which tissue planes will be treated, which facial regions are included, who provides anesthesia, where surgery occurs, and how follow-up and complication management are organized. Albert Plastic Surgery maintains a dedicated live service page for Mini Facelift. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    How to Choose deep plane facelift vs mini facelift

    Choosing a deep plane facelift vs mini facelift should begin with the areas that show aging, not with a procedure label or advertised price. During an examination, a qualified plastic surgeon evaluates skin elasticity, cheek descent, jowling, jawline definition, neck laxity, facial proportions, prior surgery, general health, and your tolerance for recovery. A Mini Facelift may be considered when laxity is mild, localized, and concentrated in the lower face. A more comprehensive deep plane operation may be discussed when tissue descent extends through the cheeks, midface, lower face, jawline, or neck. The appropriate plan cannot be determined from photographs or an online questionnaire alone.

    Ask the surgeon to describe the actual operation in anatomical terms. The word “mini” does not identify a uniform technique, and terms such as deep plane, vertical facelift, or vertical restore may be used differently among practices. Clarify the incision pattern, tissue plane, areas of elevation, expected effect on the midface and neck, treatment of excess skin, anesthesia plan, surgical facility, and follow-up schedule. If your concern includes upper-face aging, ask how the proposed facelift addresses the face as a whole rather than focusing only on the neck or jawline. A clear explanation should connect each surgical step with a specific concern identified during your examination.

    Which surgeon and facility questions deserve attention?

    When evaluating the best deep plane facelift surgeons for your needs, review credentials and technique-specific experience together. Dr. Albert is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. In consultation, ask how frequently the surgeon performs the proposed operation, how patient selection is determined, and whether photographs show patients with facial anatomy and aging patterns similar to yours. Ask how bleeding, wound-healing concerns, asymmetry, nerve-related complications, scar issues, and contour changes are managed if they occur. Marketing language should not substitute for informed discussion of limitations and risk.

    Facility and anesthesia details belong in the same review. Confirm whether surgery occurs in an appropriately accredited setting, such as one recognized by AAAASF, AAAHC, or The Joint Commission, and ask who administers and monitors anesthesia. Smoking and nicotine exposure can impair circulation and wound healing, so disclose current or past use along with medical conditions, allergies, and medications to the surgical team. Recovery plans should address swelling, bruising, numbness, incision care, activity restrictions, transportation, and access to postoperative assessment. Feeling ready to resume routine activities does not mean that visible swelling, scar maturation, or altered sensation has fully resolved.

    How should facelift cost estimates be compared?

    Comparing a deep plane mini facelift cost requires an itemized estimate rather than a single headline figure. Determine whether the quote includes the surgeon’s fee, anesthesia, facility charges, preoperative testing, garments, medications, postoperative visits, and treatment of an unexpected concern. Confirm whether the proposed surgery is a limited lower-face procedure or a broader operation involving the midface, jawline, and neck. Geographic pricing also varies, and a national fee average, even when accurately reported, does not predict a personalized New York City quote. The financial discussion should reflect the surgical plan and continuity of care, not just the shortest incision or fastest projected recovery.

    Key insight: The soundest choice is the operation that matches the distribution of facial aging, your health profile, and your expectations. Request a written plan, ask which concerns may remain untreated, and allow enough time for questions before deciding. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Frequently Asked Questions

    Is a deep plane facelift better than a Mini Facelift?

    Neither operation is universally better. A deep plane approach may be appropriate when aging affects several connected areas, such as the cheeks, midface, lower face, jawline, and neck. A Mini Facelift may be considered when laxity is milder or concentrated in the lower face. The best choice depends on anatomy, skin quality, facial proportions, health history, expectations, and the amount of correction desired. An in-person examination is needed before a surgeon can recommend a technique.

    Who may be a candidate for a Mini Facelift?

    Someone with early jowling, limited lower-face laxity, and relatively preserved cheek and neck position may be considered for this more localized operation. A Mini Facelift may not address substantial midface descent, marked neck laxity, significant skin excess, or aging distributed across the face. The word “mini” does not describe one standardized procedure, so patients should ask which tissues will be lifted, which areas will be treated, and which concerns may remain.

    Does a Mini Facelift lift the midface and neck?

    Sometimes, but the answer depends on the specific surgical design. Many limited facelifts focus primarily on the lower face and jawline. They may provide less correction in the midface or neck than a more comprehensive operation. A consultation should include a direct discussion of cheek position, nasolabial folds, neck contour, platysmal laxity, skin redundancy, and the expected boundaries of treatment. Patients should not assume that a procedure name defines its full extent.

    What are potential deep plane facelift complications?

    Possible complications include bleeding or hematoma, infection, delayed wound healing, unfavorable scars, numbness, hairline changes, asymmetry, contour irregularity, facial nerve injury, and the need for revision. Risk varies with surgical technique, anatomy, medical conditions, nicotine exposure, medications, anesthesia, and postoperative care. Contact the surgical team promptly for concerning swelling, increasing pain, fever, drainage, skin color changes, breathing difficulty, or any symptom that seems unusual after surgery.

    How long do facelift results last?

    There is no universally applicable duration for facelift results. Aging continues after surgery, and longevity is influenced by genetics, skin elasticity, weight changes, sun exposure, smoking, and general health. Swelling, bruising, numbness, and scar maturation can continue after routine activities resume. A qualified plastic surgeon can provide a more individualized recovery discussion after examining your face and reviewing your medical history.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 2, 2026 by the Albert Plastic Surgery Team
  • Deep Plane Facelift Swelling: What to Expect

    Deep Plane Facelift Swelling: What to Expect

    deep plane facelift swelling

    Swelling after a deep plane facelift is expected, temporary, and variable. It reflects the body’s healing response, not a sign that the final result will look overly tight or unnatural. Early photographs can appear unfamiliar, uneven, or more dramatic than a patient anticipated. Meaningful assessment requires time, follow-up examinations, and comparison with the preoperative plan rather than judgment based on the first several days.

    Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery is a board-certified plastic surgeon and Fellow of the American College of Surgeons. At Albert Plastic Surgery, postoperative changes are evaluated in context: incision healing, skin color, facial movement, contour, fluid accumulation, and the pattern of improvement over time. This article provides general education, not individualized medical advice. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    What is deep plane facelift swelling?

    Deep plane facelift swelling is fluid and tissue fullness that develop after surgery as the face responds to dissection and healing. Temporary changes in lymphatic drainage can contribute to edema, while inflammation around the treated tissue planes may create tightness, firmness, or an unfamiliar facial appearance. Bruising may occur at the same time, although the amount and location differ among patients. A deep plane facelift does not eliminate swelling, and claims of looking completely recovered at a specific early milestone should be approached cautiously.

    The most noticeable fullness may occur during the first several days or later in the first week, depending on the surgical plan, individual healing response, activity, sleep position, skin characteristics, and other health factors. Swelling can improve and then seem more apparent again after increased activity or as different areas heal at different rates. One side may look fuller than the other because facial anatomy, fluid movement, tissue manipulation, and sleeping position are not perfectly symmetrical. These observations require clinical context, especially when swelling is painful, rapidly increasing, associated with drainage, or accompanied by a fever or color change.

    Initial facial refinement should be judged over a longer interval than the first week or two. Serial photographs and in-person examinations offer more useful information than a single mirror image. Residual firmness, numbness, pulling sensations, and mild contour variation may gradually settle as scar tissue remodels and sensation returns. A patient who feels that the face looks “fake,” puffy, or worse before surgery during early recovery is not necessarily seeing the final outcome. The surgeon should still be informed about concerns so that normal healing can be distinguished from a complication.

    What benefits can a realistic swelling discussion provide?

    What benefits can a realistic swelling discussion provide?

    Understanding the healing process can make recovery more manageable without creating false reassurance. A patient who expects some edema is less likely to interpret every early change as a failed result. This perspective also supports practical planning for privacy, work, social commitments, transportation, and follow-up visits. Recovery remains individual, and no technique can promise a uniform timeline. The purpose of realistic counseling is to prepare a patient for variation while maintaining appropriate attention to safety.

    Deep plane facelift swelling may gradually soften as inflammation resolves and lymphatic drainage improves. That process can reveal a more natural facial contour over time, including smoother transition points along the jawline and cheek. The final appearance depends on skin elasticity, tissue quality, anatomy, surgical design, healing behavior, and the degree of laxity addressed. A facelift can reposition selected facial tissues, but it cannot stop normal aging, change every facial feature, or guarantee a particular degree of definition. Proportion and facial expression remain central to treatment planning.

    Key insight: Less visible bruising or a reduced need for drains does not mean that swelling is absent. Early appearance should be interpreted through examination findings, symptom progression, and the surgeon’s operative plan.

    Albert Plastic Surgery maintains a dedicated live service page for Mini Facelift. A Mini Facelift may be considered within the broader facelift discussion when the pattern of laxity and the patient’s goals support that approach, but it is not selected solely to avoid postoperative swelling. Technique, incision design, tissue movement, anesthesia, and expected recovery must be discussed during a consultation. The Mini Facelift page provides procedure-specific information, while an examination determines whether that option fits an individual patient.

    Patients should contact their surgical team promptly when swelling is rapidly worsening, markedly one-sided, increasingly painful, associated with shortness of breath, fever, significant redness, unusual drainage, or a sudden change in facial function. These symptoms do not establish a diagnosis through an article, yet they warrant timely medical assessment. Routine follow-up remains valuable even when recovery appears uncomplicated because subtle contour changes, incision concerns, and healing progress are best evaluated directly.

    How to Choose deep plane facelift swelling

    Choosing a facelift approach should begin with anatomy, facial laxity, skin quality, medical history, and aesthetic goals, not with a promised swelling timeline. A qualified surgeon should explain why a deep plane facelift, Nanolift™, or another facelift approach may fit the tissues being treated. The discussion should include expected edema, bruising, firmness, numbness, incision healing, activity restrictions, and the possibility that one side may settle at a different pace. No technique eliminates postoperative swelling, and a specific appearance at seven days cannot be not assured.

    During consultation, ask how the surgeon evaluates early healing and how concerns are handled between scheduled visits. A thoughtful plan includes direct examination, review of preoperative photographs, assessment of facial movement and skin color, and comparison of serial images over time. The surgeon should describe which changes are commonly observed during the first several days, what may fluctuate during the first week, and which symptoms require prompt contact. A polished recovery promise is less useful than a clear process for monitoring normal variation and identifying a possible complication.

    What should you ask before selecting a facelift approach?

    Ask whether the recommended operation addresses the specific source of visible laxity and what it cannot change. A facelift can reposition selected facial tissues and improve sagging in appropriate areas, yet it does not stop aging or guarantee a particular jawline, cheek contour, or degree of definition. Discuss the surgical plane, incision placement, anesthesia plan, anticipated scar locations, follow-up schedule, and the surgeon’s approach to asymmetry. You should also understand whether residual fullness, tightness, altered sensation, or contour irregularity could persist while healing progresses.

    Request an explanation of recovery that distinguishes milestones from deadlines. Early swelling can make the face look unfamiliar, overly full, or tighter than intended. That appearance does not determine the final result, but significant or worsening changes still deserve medical review. Ask when the surgeon generally evaluates facial refinement, how long tissue firmness may remain, and how photographs are used alongside physical examinations. If you are considering a facelift approach, ask whether its treatment area corresponds with your pattern of laxity. Mini Facelift is directly within the client-directed facelift scope. It should not be selected solely because of expectations about faster or less noticeable recovery.

    Which personal factors affect the healing course?

    Recovery varies with tissue characteristics, the extent of dissection, lymphatic drainage, baseline health, sleep position, physical activity, and adherence to the surgeon’s instructions. Smoking or nicotine exposure, uncontrolled medical conditions, and certain medications or supplements may affect surgical planning and healing. Do not change prescribed medication without guidance from the clinician managing your care. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment.

    Choose a surgeon who discusses limitations as directly as expected benefits. A safe consultation includes material risks such as bleeding, infection, fluid collection, delayed healing, nerve-related changes, unfavorable scarring, persistent asymmetry, and the possibility of revision. It should also leave room for questions about privacy, transportation, assistance at home, and access to the surgical team after the operation. The best decision is based on informed consent and a realistic understanding of the healing process, not on the shortest advertised timeline.

    Frequently Asked Questions

    How long does swelling last after a deep plane facelift?

    Swelling usually decreases progressively as inflammation settles and fluid drainage improves, but the pace differs among patients. Visible fullness may continue beyond the first one or two weeks, while firmness, mild numbness, and subtle contour changes can take longer to resolve. Final facial refinement is assessed over a longer period than the initial recovery phase. Follow-up examinations and serial photographs provide a more reliable assessment than an early mirror image.

    When is swelling usually worst?

    There is no single peak day that applies to every patient. Fullness may be most noticeable during the first several days or at another point within the first week, depending on the operation, tissue response, activity, sleep position, and individual anatomy. A timeline promising complete resolution at a fixed early milestone does not account for normal variation. Your surgeon should explain the expected pattern for your operation and tell you when a change requires contact.

    Is swelling normal seven days after surgery?

    Some remaining swelling at seven days can be part of ordinary healing. The face may still appear puffy, firm, uneven, or unfamiliar at that stage. Those features alone do not predict an unnatural final result. Swelling that is rapidly increasing, especially when paired with worsening pain, marked redness, fever, unusual drainage, skin color changes, or a sudden functional change, should be reported promptly to the surgical team.

    Can swelling increase after it initially improves?

    It can appear more prominent after activity, changes in sleep position, or normal variation in how different facial areas heal. A temporary fluctuation does not automatically indicate a problem, yet a sustained or pronounced change deserves evaluation. Do not massage the face, alter medications, or begin a new recovery measure unless your surgeon provides that instruction.

    Why does one side look more swollen than the other?

    Facial anatomy, tissue handling, lymphatic drainage, and sleeping position can contribute to temporary asymmetry. Mild differences may improve as healing progresses. Persistent, painful, rapidly developing, or clearly worsening one-sided swelling should be assessed in person. An article cannot distinguish normal asymmetry from a fluid collection, bleeding, infection, or another complication. Contact your surgeon when the appearance or symptoms concern you.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 2, 2026 by the Albert Plastic Surgery Team
  • The Complete Guide to Deep Plane Facelift Surgeons Usa

    The Complete Guide to Deep Plane Facelift Surgeons Usa

    deep plane facelift surgeons usa

    Choosing among deep plane facelift surgeons in the USA patients can trust begins with understanding the operation, not with a marketing label. A deep plane facelift is a form of facelift surgery that repositions deeper facial tissues to address age-related descent in the cheeks, jowls, and selected areas of the neck. The appropriate technique depends on facial anatomy, skin quality, tissue movement, medical history, and the result a patient hopes to achieve.

    Key Takeaways

    • A deep plane facelift works below the superficial layers, lifting cheek and jowl tissue at its foundation to correct the downward drift that develops with age.
    • Patients should evaluate a surgeon's understanding of the anatomy and technique rather than relying on advertising language when comparing providers across the country.
    • The right surgical approach is never one size fits all, since skin quality, tissue mobility, medical background, and personal goals all shape the operative plan.
    • Improvement in the cheeks, jowls, and neck comes from repositioning deeper structures, which is why this technique can produce results that look natural over time.

    Dr. Mark G. Albert, MD, FACS of Albert Plastic Surgery is the practice’s founder. He is certified by the American Board of Plastic Surgery and a Fellow of the American College of Surgeons. This article provides general education only. Candidacy, technique, anesthesia, recovery, risks, and outcomes require individualized clinical assessment with a qualified plastic surgeon.

    What is deep plane facelift surgeons usa?

    A deep plane facelift is performed beneath the superficial muscular aponeurotic system, commonly called the SMAS, within a deeper anatomical layer of the face. This approach may allow the surgeon to mobilize and reposition connected facial soft tissues rather than relying on skin tension alone. The goal is a refreshed, proportionate appearance that preserves individual expression and avoids an overly tight look. A deep plane facelift does not correct every concern involving the face, and it is not automatically better than a SMAS facelift, composite facelift, or Mini Facelift.

    During planning, a surgeon evaluates the midface, cheek descent, nasolabial folds, jowls, jawline, neck contour, skin elasticity, facial volume, and soft-tissue laxity. Skin texture and sun damage can affect the visible finish, while deeper repositioning addresses structural descent. A deep plane facelift may suit some adults with moderate to advanced lower-face or midface laxity, yet age alone does not establish candidacy. Medical conditions, tobacco or nicotine use, medication history, healing capacity, and expectations must be reviewed in person.

    Key insight: The name of a facelift technique is only one part of the decision. Surgical judgment includes layer selection, incision design, preservation of facial anatomy, management of the neck when appropriate, anesthesia planning, and a careful assessment of how the result will relate to the eyes, brow, lips, and overall face.

    Benefits of deep plane facelift surgeons usa

    Benefits of deep plane facelift surgeons usa

    The potential benefit of a deep plane facelift is improvement in facial contour through deeper tissue repositioning. Depending on anatomy, treatment may soften cheek descent, reduce the appearance of jowls, define the mandibular border, and improve selected neck changes. Releasing and redraping deeper retaining structures can reduce the need to pull the skin tightly. This may support a more natural transition from the cheek to the jawline, though the final appearance varies with tissue quality, healing, surgical design, and individual anatomy.

    Deep plane surgery may also help address the connection between the midface and lower face in patients whose aging changes extend beyond isolated skin laxity. A carefully planned operation considers facial balance rather than focusing on one fold or contour. The brow and eyes remain part of the overall assessment, even when the planned operation is limited to facelift surgery. A facelift does not directly correct every upper-face concern, and a surgeon should explain those boundaries before surgery.

    Patients often seek this approach because they want to look rested while still looking like themselves. That objective requires restraint. A deep plane facelift cannot stop future aging, remove every wrinkle, correct poor skin elasticity, or guarantee a particular degree of longevity. It also carries meaningful risks, including bleeding, infection, fluid collection, scarring, sensory changes, facial nerve injury, asymmetry, contour irregularity, hairline or earlobe changes, and the possibility of revision. The risk profile depends on the patient, technique, anesthesia, and surgical facility.

    A Mini Facelift is a distinct facelift option that may be considered when laxity is more limited and the treatment plan can be appropriately smaller in scope. It is not a substitute for deeper surgery in every patient. The meaningful question is whether the chosen operation matches the location and degree of tissue descent, skin characteristics, neck findings, and the patient’s goals. Consultation with a board-certified plastic surgeon is necessary before making that determination.

    How to Choose deep plane facelift surgeons usa

    Choosing deep plane facelift surgeons usa patients can evaluate responsibly requires more than reviewing photographs or reading a procedure description. Begin with credentials, operative judgment, and the quality of the consultation. A surgeon performing facelift surgery should be certified by the American Board of Plastic Surgery, which indicates completion of defined training and examination requirements in plastic surgery. Patients can verify certification through the American Board of Plastic Surgery. Medical licensure, board certification, hospital privileges, fellowship training, and facility accreditation each provide different information and should not be treated as interchangeable.

    Dr. Albert founded Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and a Fellow of the American College of Surgeons. FACS identifies membership in a professional organization whose requirements include training, ethical standards, professional standing, and ongoing review. It is an authority signal, not a promise of a particular result. Aesthetic plastic surgery fellowship training can add focused experience, yet patients should still ask how the surgeon evaluates anatomy, selects a tissue plane, manages the neck when appropriate, and addresses facial balance.

    Which questions should you ask during a facelift consultation?

    A useful consultation should be an anatomical discussion rather than a sales presentation. Ask which areas the proposed operation is intended to address, such as cheek descent, nasolabial folds, jowls, jawline definition, or neck laxity. Ask what the technique cannot correct, how skin quality may affect the visible result, and how the plan accounts for the relationship among the brow, eyes, cheeks, lips, and lower face. A surgeon should explain incision placement, scar maturation, facial nerve considerations, anesthesia, facility setting, follow-up, and possible revision without presenting any outcome as not assured.

    Before selecting among deep plane facelift surgeons usa patients should review before-and-after photographs with attention to natural expression, facial proportions, ear and hairline position, neck contour, and consistency across different patients. Photographs cannot predict an individual result, and lighting, posture, image selection, and follow-up timing affect interpretation. Request a written estimate that identifies surgeon fees, anesthesia, facility charges, postoperative visits, and any items excluded from the quoted amount. Cost alone does not establish quality, and a practice should be able to explain its estimate clearly.

    Safety planning deserves specific attention. Ask whether surgery occurs in an appropriately accredited facility, who provides anesthesia, how medical conditions and medications are reviewed, and how urgent concerns are handled after discharge. Meaningful risks include bleeding, infection, fluid collection, unfavorable scarring, numbness, asymmetry, contour irregularity, delayed healing, and facial nerve injury. Nicotine exposure, uncontrolled medical conditions, bleeding tendencies, and unrealistic expectations may affect eligibility or timing. A qualified clinician must determine whether surgery is reasonable after reviewing your health history and examining your face in person.

    Frequently Asked Questions

    What is a deep plane facelift?

    A deep plane facelift repositions facial soft tissue beneath the SMAS layer, a connective tissue structure associated with facial movement and support. The operation may address descent involving the cheeks, jowls, jawline, and selected areas of the neck. The technique is not automatically appropriate for every patient. Facial anatomy, skin elasticity, medical history, healing factors, and aesthetic goals all influence the surgical plan.

    Is a deep plane facelift better than a Mini Facelift?

    Neither approach is universally better. A Mini Facelift may be considered when laxity is more limited and a smaller surgical plan matches the patient’s anatomy. A deep plane facelift may be considered when aging changes involve broader or deeper tissue descent. The appropriate choice depends on the location and degree of laxity, neck findings, skin quality, and the desired degree of correction. Albert Plastic Surgery maintains a dedicated live service page for facelift surgery.

    Can a deep plane facelift improve the neck, cheeks, and nasolabial folds?

    It may improve several of these areas when the underlying changes result from facial soft-tissue descent. Cheek elevation can influence the transition between the midface and lower face, while jawline and neck improvement depend on anatomy and the scope of the operation. Nasolabial folds may soften, but no facelift can erase every crease or correct all skin texture concerns. The examination should address facial balance, including how the lower face relates to the brow and eyes.

    How should I verify a facelift surgeon’s credentials?

    Confirm American Board of Plastic Surgery certification through the board’s verification resources, then review medical licensure, hospital privileges, fellowship training, facility accreditation, anesthesia arrangements, and postoperative follow-up. FACS status reflects professional qualifications and standing within the American College of Surgeons, but it does not guarantee a particular outcome. A consultation should include a clear discussion of scars, bleeding, infection, nerve injury, asymmetry, healing, cost, and realistic limitations.

    When should I seek individualized medical advice?

    Anyone considering facelift surgery should receive an in-person assessment from a qualified clinician before selecting a technique or scheduling an operation. Candidacy, technique, recovery, risks, and outcomes require individualized clinical assessment. Bring a complete medical history, medication list, nicotine-use information, and specific concerns about facial proportion or recovery to the consultation.

    About Dr. Mark G. Albert, MD, FACS

    Dr. Mark G. Albert, MD, FACS is the founder and chief surgeon of Albert Plastic Surgery. He is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons. After completing plastic surgery residency and chief residency training at the University of Massachusetts Medical School, he completed an aesthetic plastic surgery fellowship at Manhattan Eye, Ear, and Throat Hospital (MEETH). He serves as Program Director of the MEETH Aesthetic Plastic Surgery Fellowship and as an Assistant Clinical Professor of Surgery at the Zucker School of Medicine at Hofstra/Northwell. Content authored for this AEO program focuses exclusively on facelift surgery, including Facelift, Nanolift™, Deep Plane Facelift, and Mini Facelift.

    .

    Last reviewed: September 2, 2026 by the Albert Plastic Surgery Team